What’s the Anion Gap?
The anion gap is a calculated value used to evaluate acid-base balance and identify certain types of electrolyte imbalance. It contrasts the main measured cations and measured anions in blood chemistry, especially sodium and chloride, along with bicarbonate-related values. Clinicians use it as part of a more complete review at serum chemistry and overall clinical interpretation.
Although the body contains many ions, routine testing relies on a few key laboratory values. The anion gap helps estimate whether unmeasured acids may be present in excess. That makes it a useful diagnostic tool and screening test in the evaluation of metabolic acidosis and other acid-base disorder patterns.
In practice, the anion gap is not a direct measurement. It is a derived number that aids patient evaluation by giving context to a chemistry panel. When interpreted correctly, it can point toward an underlying cause of illness and direct the next steps in an anion gap assessment.
How an Anion Gap Calculator Functions
An anion gap calculator relies on results commonly reported on a basic metabolic panel. It typically takes serum sodium, serum chloride, and serum bicarbonate to yield a calculation result. Some versions also allow entry of potassium, which marginally changes the outcome.
The purpose of the calculator is to streamline the calculation formula and minimize manual error. This is helpful when reviewing rapid test results, tracking trends over time, or performing a fast interpretive guide during clinical decision-making. Because the anion gap is a derived metric, the quality of the input values matters. Inaccurate or outdated laboratory values can cause misleading results.
Most calculators are designed for simple use:
- Type in the sodium value from the chemistry panel. Enter the chloride value. Enter the bicarbonate value. Optionally enter potassium if the formula includes it. Review the resulting anion gap and compare it with the expected reference interval.
Used correctly, this diagnostic tool aids fast recognition of a metabolic derangement. But the number itself is only one piece of the puzzle. Interpretation should always include the patient’s symptoms, clinical setting, and the possibility of measurement issues or shifts in protein levels.
Anion Gap Formula and Normal Range
The typical anion gap formula is often written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some laboratories and calculators include potassium in the equation:
Anion gap = (Sodium + Potassium) − (Chloride + Bicarbonate)
Both version measures the disparity between key measured ions and helps identify unmeasured substances in the blood. Because different labs use different methods, the normal anion gap can vary slightly. For that reason the local reference range is more important than a single universal number.
In many settings, the normal anion gap is evaluated in the context of the lab’s specific reference interval. This range may differ depending on whether potassium is included and on the analyzer used for testing. A result that looks abnormal in one setting may be appropriate in another, so the interpretation should follow the reporting lab’s standards.
The concept of “normal” also relies on physiology. The anion gap reflects the balance between unmeasured acids and unmeasured bases, and it can shift with changes in albumin or other proteins. For this reason a seemingly modest change can still matter clinically if the overall picture suggests acid-base balance has been disrupted.
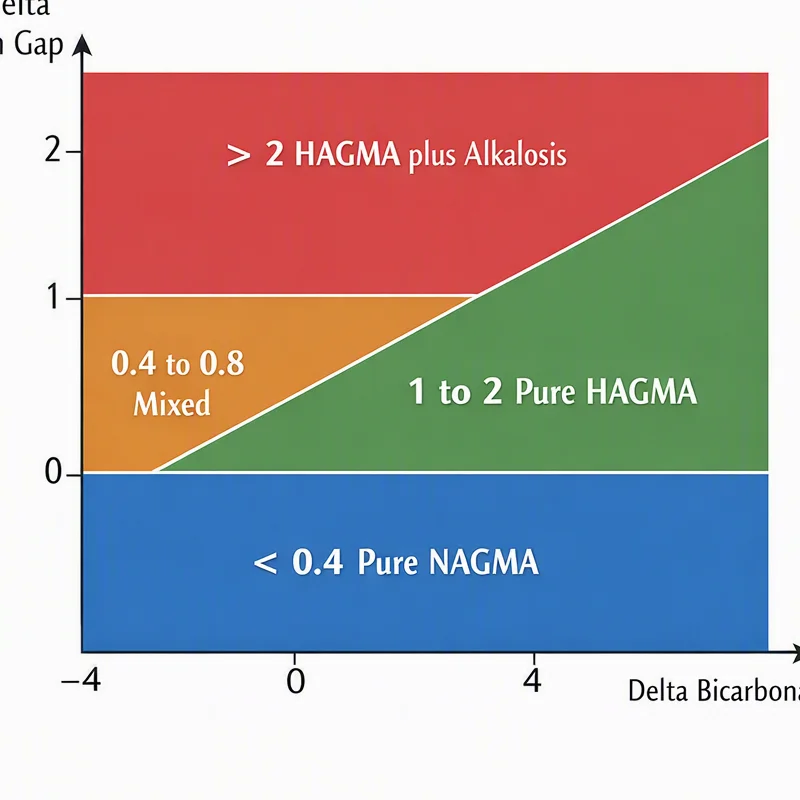
How to Understand a Raised Anion Gap
A high anion gap often indicates the presence of additional unmeasured acids in the bloodstream. The classic anion gap in chronic kidney disease concern is acidotic imbalance, especially high anion gap metabolic acidosis. In this setting, the body has accumulated acid faster than it can clear it, or it has lost bicarbonate while retaining acid equivalents.
Common causes include lactate buildup, ketone buildup, kidney failure, toxic alcohols, and salicylate poisoning. Each of these conditions can increase the number of unmeasured anions or alter how the body handles acid. The lab result is therefore a clue, not a diagnosis by itself.
Lactic acidosis occurs when lactate accumulates, often during poor tissue perfusion, severe infection, intense exertion, or other states of reduced oxygen delivery. Ketone buildup is seen when ketone bodies rise, such as in uncontrolled diabetes, prolonged fasting, or heavy alcohol use. Both conditions can cause a significant rise in the anion gap and require prompt assessment.
Kidney failure can also cause a high anion gap because the kidneys are less able to remove acids and other metabolic byproducts. Toxic alcohol ingestion, including substances such as methanol and ethylene glycol, generate acidic metabolites that raise the gap. Salicylate poisoning may produce a mixed acid-base pattern, so the anion gap must be interpreted alongside other findings.
When a high result appears, clinicians often ask whether there is an identifiable root cause of acidosis. The answer usually comes from combining the calculator output with the patient’s symptoms, history, and additional testing. That makes the anion gap a valuable diagnostic significance marker in a broader workup.
How to Interpret a Low Anion Gap
A low anion gap is not as common than a high one, but it should never be overlooked. It may indicate changes in unmeasured proteins, unusual lab conditions, or sometimes a serious disease process. One of the main explanations is hypoalbuminemia, because albumin is a major negatively charged protein in the blood.
Multiple myeloma can also be associated with a low anion gap, because abnormal proteins may alter the balance of measured and unmeasured ions. In this setting, the result may suggest a plasma protein abnormality rather than a classic acid buildup. That is why the anion gap should be considered in the context of the entire clinical picture.
Laboratory error is another common explanation and should always be considered first, especially if the value is unexpected or inconsistent with the patient’s condition. Problems with specimen handling, analyzer calibration, or transcription can all create misleading results. Repeating the test can help confirm whether the result is real.
Other causes may include significant shifts in albumin, exposure to certain medications, or changes in the balance of cations and anions that affect the measurement. A low value does not always mean danger, but it does require thoughtful review. The goal is to determine whether the number reflects physiology, a technical issue, or a condition requiring treatment.
Typical Causes of an Abnormal Anion Gap
An abnormal anion gap can occur for various reasons, and the result often indicates a broader metabolic problem rather than a single disease. In general, the major categories include too much acid production, impaired acid elimination, protein abnormalities, and measurement issues. Looking at the pattern alongside albumin and other chemistry results increases accuracy.
For a high value, the most common causes are metabolic acidosis, lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. For a low value, hypoalbuminemia, multiple myeloma, and laboratory error are major possibilities. Less common causes may involve uncommon toxins, medications, or shifts in electrolytes.
The key point is that the anion gap is a clue to acid-base disorder, not a final diagnosis. A result above or below the expected range should trigger questions about symptoms, medication use, kidney function, nutritional status, and possible toxic exposures. This is why the test is most valuable when paired with overall patient evaluation.
How Albumin Influences the Anion Gap
Albumin stands as one of the main hidden negative ions in blood. Since it has a negative charge, lower levels of serum albumin can lower the measured anion gap even when acid-base status is altering. This is why a raw calculator result may downplay the true degree of metabolic disturbance.
Albumin correction adjusts the calculation to account for low protein levels. The goal is delta ratio calculation example to derive a corrected value that better reflects the patient’s actual chemistry. This is especially useful when evaluating a person with illness, malnutrition, liver disease, inflammation, or other conditions that can deplete albumin.
A common interpretation principle is that low albumin can mask a high anion gap. Without correction, a patient with significant acid accumulation could look like they have a near-normal result. That is why the corrected anion gap can be more revealing than the unadjusted number in selected cases.
Protein levels matter because they influence the overall balance of charged particles in the blood. When albumin drops, unmeasured anions decrease, and the calculated gap may drop even if the underlying acid problem persists. In practice, albumin correction improves the quality of clinical interpretation and reduces the chance of missing an important acid-base disturbance.
Stepwise Illustrative Calculation
This is a straightforward sample calculation based on standard laboratory values:
- Sodium: 140 Cl: 102 Bicarbonate: 24
Using the common formula:
Anion gap = Na − (Chloride + HCO3)
Plug in the numbers:
Anion gap = 140 − (102 + 24)
Begin by combining the chloride value and bicarbonate:
102 + 24 = 126
After that take away from sodium:
140 − 126 = 14
The computed value is 14. Whether that is considered normal depends on the laboratory’s reference interval. In cases where the lab’s normal anion gap range includes 14, the result may be acceptable. If the lab uses a lower upper limit, it may be borderline high. This is why the calculator output must always be matched to the reported range.
When the same patient had low albumin, the corrected value might be higher than 14 after albumin correction. Such a change could reveal a hidden metabolic acidosis. This brief calculation shows how the calculator supports both quick review and deeper anion gap assessment.
When to Get Medical Evaluation
An abnormal anion gap should be taken seriously when it appears with concerning symptoms or other abnormal labs. Signs such as confusion, rapid breathing, severe weakness, vomiting, dehydration, chest pain, or reduced consciousness may point to a significant acid-base disorder. In these situations, prompt review by a clinician is important.
Emergency evaluation may be needed if the person has possible toxin exposure, severe hyperglycemia, signs of shock, kidney failure symptoms, or rapidly worsening illness. Because the anion gap is only one piece of the puzzle, the broader clinical context determines urgency. A concerning result combined with serious symptoms should not wait.
Without emergency warning signs, ongoing abnormal findings need follow-up. A clinician may repeat the basic metabolic panel, run further blood tests, check serum albumin, or investigate possible causes such as infection, diabetes, renal dysfunction, or toxic exposure. The aim is to identify the underlying cause and address the metabolic problem before complications develop.
Frequently Asked Questions: Anion Gap Calculator and Interpretation
What counts as a normal anion gap?
The normal range for the anion gap depends on the laboratory and the formula used. Because some methods include potassium and others do not, the reference interval can vary. The most reliable approach is to compare the calculator result with the value reported by the testing lab for accurate interpretation.
How do you work out the anion gap?
The standard anion gap formula is sodium − (chloride + bicarbonate). Some calculators include potassium as well. An anion gap calculator simplifies this process by using the values from a chemistry panel to deliver an immediate result and aid clinical interpretation.
What does a high anion gap suggest?
A high anion gap typically indicates excess unmeasured acids and may indicate metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. The result should be evaluated with symptoms and other laboratory findings to identify the cause.
Can a low anion gap matter?
It can, a low anion gap can sometimes be important, especially if it is persistent or unexplained. It may be linked to hypoalbuminemia, multiple myeloma, or laboratory error. If the result is unexpected, it should be reviewed carefully and repeated if needed.
Why does the albumin change the anion gap?
The albumin protein is a principal negatively charged protein in blood, so lower levels decrease the number of unmeasured anions. That can make the anion gap appear smaller than it really is. Correcting for albumin helps determine a more accurate adjusted value and helps improve the detection of hidden acid-base disorder.