What Is the Anion Gap?
The anion gap is a computed value used to support the assessment of acid-base status and identify certain types of metabolic acidosis. It reflects the gap between the measured positively charged and negative ions in the blood, especially the main electrolytes found on a routine chemistry panel. In clinical practice, the anion gap helps clinicians detect hidden acids or other unmeasured ions that may not be readily visible from routine laboratory values alone.
The most commonly measured sodium, chloride, and bicarbonate values are the foundation of the calculation. These results come from a standard electrolyte panel or serum chemistry test. Because the body must maintain tight acid-base balance, even small shifts in these values can offer useful clues about a broader metabolic disorder or systemic illness.
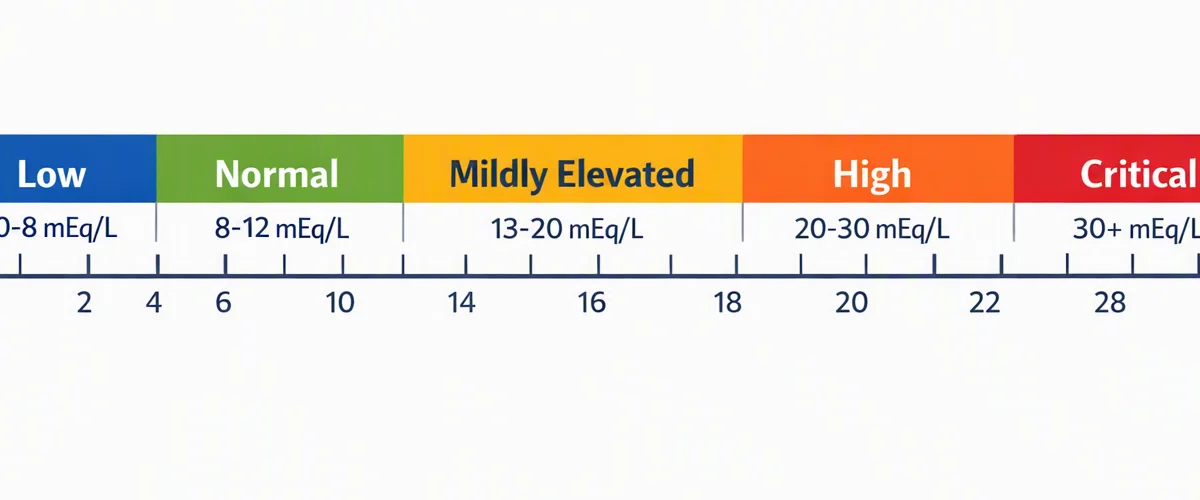
Although the anion gap is not a standalone diagnosis, it is a important diagnostic tool for screening and cause identification. A normal or abnormal result should always be viewed in clinical context rather than in isolation.
In what way the Anion Gap Calculator Works
An anion gap calculator uses the anion gap formula to perform a straightforward calculation from your lab results. The classic version is:
Anion gap = Sodium − (Chloride + Bicarbonate)Some providers also add potassium in the formula, particularly in older teaching models or special cases:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)Most contemporary reading relies on the sodium-based formula without potassium, but either method is valid if you stay consistent with the same reference range and interpretation approach. The calculator simply compiles the numbers from the serum chemistry panel and carries out the arithmetic, which saves time and minimizing transcription errors.
Typical inputs include:
- Sodium Chloride Bicarbonate Sometimes potassium
As the result is based entirely on these lab values, the calculator is only as precise as the underlying measurements. It is a convenient shortcut, but it does not replace professional interpretation, especially when the patient has complicated acid-base physiology or multiple abnormalities at once.
Standard Anion Gap Range and Meaning
The reference range for the anion gap depends on the testing method and whether potassium is included. Various analyzers and analytic methods can shift the expected reference range, so the accurate interpretation should always use the lab’s own published range. In many settings, a typical sodium-based anion gap is roughly in the lower teens, but the exact cutoff varies.
A normal anion gap does not automatically mean everything is normal, and an elevated value does not tell you the cause by itself. Instead, the result should be used as a clue in the broader evaluation of acid-base disorders. One of the most important uses is distinguishing between metabolic acidosis with excess unmeasured acids and acidosis caused by direct bicarbonate loss or chloride gain.
In general, interpretation follows this pattern:
- Normal anion gap: often seen when bicarbonate loss is balanced by chloride increase. High anion gap: suggests extra unmeasured acids in the blood. Reduced anion gap: less common, but may occur with low albumin, lab issues, or unusual ions.
The result becomes much more meaningful when compared with the patient’s symptoms, medication history, acid-base balance, and other serum chemistry findings.
Elevated Anion Gap Metabolic Acidosis Reasons
Elevated anion gap metabolic acidosis occurs when the blood holds extra acids that are not directly measured by the standard electrolyte panel. These unseen acids lower bicarbonate while increasing the gap between sodium and the sum of chloride plus bicarbonate. This pattern is one of the most important signals in acid-base evaluation.
Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Each cause reflects a different mechanism of acid accumulation:
- Lactic acidosis: rise of lactate due to poor tissue oxygen delivery, shock, severe infection, seizures, or other stress states. Ketoacidosis: accumulation of ketones, often related to diabetes, starvation, or alcohol use. Renal failure: reduced kidney ability to clear acids and regenerate bicarbonate. Toxic ingestions: substances such as methanol, ethylene glycol, salicylates, or other poisons can create dangerous acid-base changes.
Since these disorders can signal serious illness, a high anion gap should prompt rapid evaluation of the patient’s clinical status. The size of the gap can help with severity assessment, but the exact diagnosis still depends on the full picture, including symptoms, vital signs, and additional laboratory testing.
Typical Anion Gap Metabolic Acidosis Reasons
Normal anion gap metabolic acidosis is also https://anion-gap-checker101.scriblorax.com/posts/anion-gap-calculator-for-children-how-to-interpret-results called hyperchloremic acidosis because chloride often rises as bicarbonate falls. In this situation, the body loses bicarbonate or fails to regenerate it properly, but the change is offset by an increase in chloride, so the overall anion gap remains within the normal range.
Two common causes are loose stools and tubular kidney acidosis. Diarrhea causes direct loss of bicarbonate from the gastrointestinal tract. Renal tubular acidosis occurs when the kidneys cannot handle acid secretion or bicarbonate reabsorption effectively. In both settings, the change is often visible on the electrolyte panel as a falling bicarbonate level with a relative chloride increase.
Other contributors may include certain intravenous fluids, kidney disorders, and medications that affect acid handling. The key concept is that the body is losing bicarbonate rather than accumulating a large amount of unmeasured acid. That distinction is central to the interpretation of acid-base status.
Albumin Correction and Its Clinical Importance
Serum albumin is among the most important negative charges not directly measured in the blood. When albumin is low, the measured anion gap may seem falsely normal or only mildly elevated even when a true acid load is present. This is why correcting albumin matters.
The adjusted anion gap refines the result for reduced albumin. Since albumin carries a negative charge, lower levels decrease the expected gap. Without correction, a patient with low albumin may have an underestimated gap and a missed clue to metabolic acidosis.
This refinement is especially important in hospitalized patients, critically ill patients, or anyone with poor nutrition, inflammation, liver disease, kidney disease, or other causes of reduced protein. In those settings, using the corrected value gives a more accurate comparison against the expected reference range and improves cause identification.
A practical approach is to remember that albumin is part of the chemistry behind the calculation, even though it is not in the basic formula. The anion gap calculator may show both the uncorrected and corrected result so that interpretation is more reliable.
Step-by-Step Instructions to Operating the Calculator
Using the calculator is straightforward if you input the correct serum sodium, serum chloride, and serum bicarbonate results from the same blood sample. Exact matching of the numbers counts because even small timing differences can affect the calculation.
Use these instructions:
- Input the serum sodium value from the chemistry panel. Provide the serum chloride value. Enter the serum bicarbonate value, occasionally reported as CO2 or total CO2. If prompted, add potassium for a potassium-inclusive calculation. Check the output and see how it compares with the lab’s reference range. If albumin is available, apply albumin correction to determine the corrected anion gap.
The calculation itself is straightforward, but the real value comes from weighing the result with the patient’s symptoms and other findings. Think of the calculator as a quick way to organize serum chemistry information, not as a replacement for clinical evaluation.
Understanding Values Alongside the Clinical Picture
The gap is most helpful when combined with an arterial blood gas, particularly if the acid-base problem is multifactorial. The blood gas provides the pH, carbon dioxide level, and evidence of respiratory compensation. In combination with the anion gap, it helps distinguish primary metabolic from respiratory processes and confirms whether there is true acidemia or alkalemia.
Other important markers include base deficit, which shows the magnitude of metabolic acid burden, and the overall trend in bicarbonate. A low bicarbonate with a high anion gap is consistent with a diagnosis of high-gap metabolic acidosis, but a mixed process can obscure the pattern.
Interpretation should always answer a few key issues:
- Is the patient acidotic on the blood gas? Does the chemistry panel show a high or normal gap? Is there evidence of compensation or a mixed disorder? What clinical findings suggest the underlying diagnosis?
This approach ties the number to the bedside picture. For example, severe illness with elevated lactate points toward lactic acidosis, while hyperglycemia or starvation may point toward ketoacidosis. Kidney dysfunction may suggest renal failure as the cause, while exposure history may raise concern for toxic ingestions.
Frequent Pitfalls and Limitations
Although the anion gap is valuable, it has important limitations. One common issue is lab error. Since the result comes from multiple measured electrolytes, any problem in specimen handling, analyzer performance, or transcription can distort the final value. Unexpected results should be repeated if they do not fit the clinical picture.
A mixed acid-base disorder can also mask the expected pattern. For example, a patient may have metabolic acidosis plus metabolic alkalosis, or metabolic acidosis plus respiratory compensation that does not fit the usual pattern. In those cases, the gap alone may not fully show how sick the patient is.
Ionized calcium is an additional element that can affect the broader interpretation of acid-base physiology, even though it is not part of the formula. Variations in calcium balance may matter in critical illness and may influence the overall evaluation.
Medications can also alter acid-base balance or electrolyte patterns. Some drugs lead to acidosis, raise chloride, interfere with kidney function, or change the expected laboratory profile. Because of these limitations, the anion gap should be treated as one component of the diagnostic puzzle rather than the anion gap in chronic kidney disease whole diagnosis.
In short, the calculator is a useful interpretation aid, but not a single decision-maker. The most reliable use comes from combining the number with serum albumin, blood gas data, history, medication review, and full clinical context.
FAQs About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used to efficiently perform the anion gap calculation from routine electrolyte values. It helps evaluate acid-base status, check for metabolic acidosis, and assist cause identification when the result is abnormal. It is especially useful when reviewing serum chemistry or an electrolyte panel in a patient with suspected acid-base problems.
What is the normal anion gap range?
The normal range depends on the laboratory and its measurement method, so the best answer is the lab’s own reference range. Many labs report a sodium-based anion gap in the low teens, but the exact number can differ. Always interpret the result using the range provided by the testing facility.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. In other words: sodium − (chloride + bicarbonate). Some versions also include potassium, but the sodium-based version is most commonly used. The values should come from the same blood sample to keep the calculation accurate.
Why should you correct the anion gap for albumin?
You adjust the anion gap for albumin because serum albumin is a major unmeasured anion. When albumin is decreased, the measured gap may appear falsely normal. The corrected anion gap helps account for hypoalbuminemia and offers a more accurate reading of possible metabolic acidosis.
What does a raised anion gap suggest in acid-base status?
A high anion gap usually indicates high anion gap metabolic acidosis, meaning there are more unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. The result should be read with the arterial blood gas, pH, bicarbonate level, and the overall clinical picture to support the diagnosis.