How does one define an Anion Gap Calculator?
An anion gap calculator is a straightforward assessment tool used to determine the variation between measured electrolytes in the blood, usually based on sodium, chloride, and bicarbonate. This calculated value helps determine whether there is an anion gap rise suggestive of metabolic acidosis and related patterns of acid-base imbalance.
In basic serum chemistry interpretation, the calculator supports clinical interpretation by helping detect whether there is an accumulation of unmeasured acid in the bloodstream. Because the body normally maintains tight acid-base balance, even slight shifts in laboratory values can suggest an important metabolic derangement.
The main strength of an anion gap calculator is its diagnostic utility. It does not confirm a condition by itself, but it provides a rapid way to screen for high anion gap metabolic acidosis, triggering further review of the patient’s symptoms, medications, and possible causes of acid accumulation.
In practice, the calculator is often used together with the broader anion gap formula, other laboratory values, and the overall clinical picture. That includes looking for signs of electrolyte imbalance, dehydration, and acid-base disturbance that may require timely evaluation.
How the Anion Gap Connects to Alcoholic Ketoacidosis
Alcoholic ketoacidosis is a form of medical emergency that can occur after heavy alcohol use, poor intake, and frequent vomiting. The condition is defined by increased ketone production, especially when the body shifts away from glucose use and into fat metabolism. This leads to the buildup of acidic ketones, including beta-hydroxybutyrate, which can increase the anion gap.
In alcoholic ketoacidosis, the blood often shows ketonemia with increased concentrations of ketones, but the pattern may be subtle if only urine ketones are checked. Beta-hydroxybutyrate is especially significant because it is frequently the main ketone in this condition. As these acids accumulate, they consume bicarbonate, reducing bicarbonate and resulting in metabolic acidosis.
This is why the anion gap calculator is so useful in this setting. A high value can reinforce suspicion for high anion gap metabolic acidosis, especially when combined with the patient’s history, volume status, and other laboratory findings. It can also be used to separate alcoholic ketoacidosis from other causes of acidosis that may look similar at first glance.
Alcoholic ketoacidosis often appears in the setting of volume depletion, poor oral intake, and ongoing vomiting. Those factors can worsen acid-base changes and make interpretation more complex. In some cases, the patient may have a mixed acid-base disorder, meaning more than one process is affecting the final pH.
How to Calculate the Anion Gap
The common approach to calculating the anion gap uses sodium, chloride, and bicarbonate. The typical calculation is:
Anion gap = sodium - (chloride + bicarbonate)
These results are usually taken from a basic metabolic panel or other serum chemistry panel. A higher than expected result suggests that unmeasured anions may be present in the blood, which is why the calculator is helpful for checking acid-base disorders.
Albumin also plays a role because it is a key unmeasured anion. When albumin is low, the measured anion gap can appear falsely normal or only mildly elevated. For that reason, lab result interpretation should consider whether an albumin-corrected anion gap is needed.
To use the calculator well, it helps to review each component carefully:
- Sodium reflects the main measured cation in the formula. Chloride and bicarbonate are the main measured anions included in the calculation. Albumin affects the expected baseline and may change the interpretation.
Because subtle changes in these laboratory values can shift the result, clinical interpretation should never rely on the number alone. A patient with alcoholic ketoacidosis may have a distinctly abnormal anion gap even before severe pH changes are obvious.
Anion Gap Formula and Albumin Correction
The anion gap formula is simple, but analysis becomes more nuanced when albumin is low. Since hypoalbuminemia reduces the baseline anion gap, the uncorrected result may miss the true degree of acid-base disturbance.
That is why an albumin-corrected anion gap is often important. Accounting for albumin enhances the corrected anion gap estimate and can reveal a clinically important gap that would otherwise be missed. This can be significant in patients with poor nutrition, chronic illness, or heavy alcohol use, where low albumin may be common.
A typical reference range for the anion gap varies depending on the laboratory method and whether potassium is included in the formula. The specific cutoffs can change by institution, so interpretation should always use the local reference range rather than assuming one universal normal value.
In alcoholic ketoacidosis, albumin correction can be especially useful because the patient may have multiple contributors to acid-base imbalance. A low albumin level may mask the severity of the high anion gap metabolic acidosis, making the corrected result more informative for clinical interpretation.
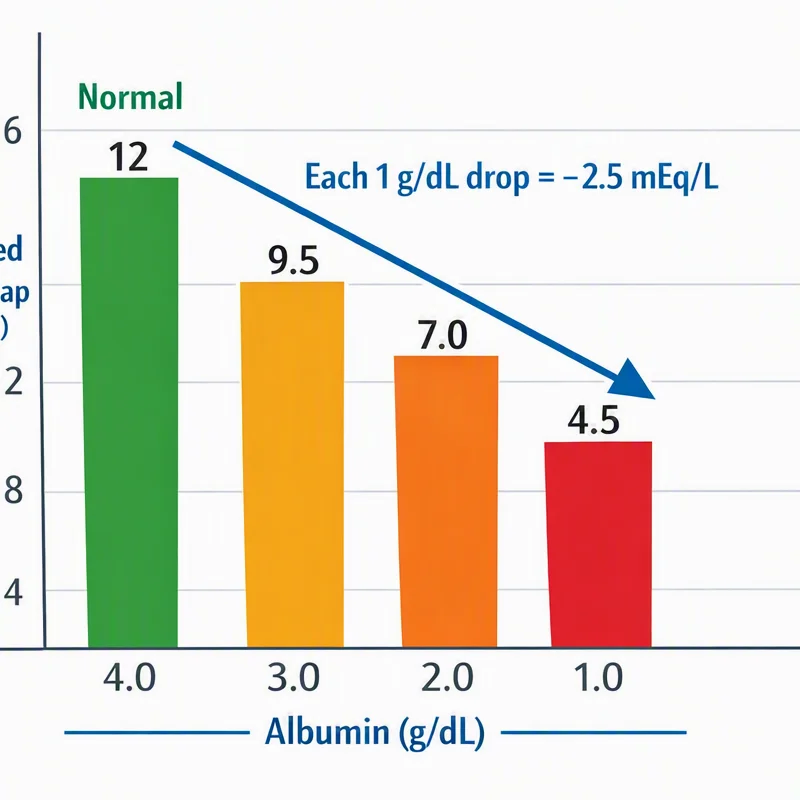
Key point: A normal-looking anion gap does not always eliminate a significant acid-base disorder if albumin is low or if a mixed process is present.
Typical Laboratory Findings for Alcoholic Ketoacidosis
Alcoholic ketoacidosis commonly creates a recognizable pattern of lab results, though not all patient demonstrates the same picture. The core abnormality is usually elevated beta-hydroxybutyrate, which signals active ketone production and supports the diagnosis of ketonemia.
Glucose may be low, within normal limits, or only somewhat elevated. This helps distinguish alcoholic ketoacidosis from diabetic ketoacidosis, where glucose is frequently much higher. However, similarity can occur, so glucose alone should not be used as the single discriminator.
Lactate may also be raised, especially if there is hypoperfusion, volume depletion, or impaired metabolism. That means some patients have both ketoacidosis and lactic acidosis, which can deepen the high anion gap. Lactate elevation does not exclude alcoholic ketoacidosis; it may simply add another layer of acid accumulation.
Common findings may include:
- Increased beta-hydroxybutyrate Presence of ketonemia Low bicarbonate High anion gap Variable glucose level Possible lactate elevation
The set of these laboratory values backs up the diagnosis, but the clinical context remains vital. Symptoms such as vomiting, poor intake, and recent alcohol cessation are especially important in recognizing the underlying metabolic derangement.
How to Read Findings Carefully
Careful interpretation of the anion gap requires moving past the calculator result and considering the complete acid-base picture. A patient may have a high anion gap and still have a near-normal pH if another process is also present. That is the hallmark of a mixed acid-base disorder.
For example, vomiting can produce metabolic alkalosis from loss of gastric acid while alcoholic ketoacidosis results in metabolic acidosis. The net pH may appear less abnormal than expected. Because of that, a normal or only slightly abnormal pH should not outweigh other evidence of a serious acid-base disturbance.
An arterial blood gas can help determine whether there is true acidemia, compensation, or an additional respiratory component. Blood gas data, together with serum chemistry, strengthens lab result interpretation and helps identify the full pattern of metabolic acidosis.
The osmolar gap is another helpful piece of information when the diagnosis is uncertain. An elevated osmolar gap may raise concern for toxic alcohol ingestion, especially if the history is unclear. In that setting, the anion gap calculator helps with differential diagnosis, but it should be used as part of toxin screening and broader evaluation rather than as a standalone answer.
Clinical interpretation is safest when all of the following are considered together:
- Symptoms and history Serum chemistry results Arterial blood gas Albumin level Osmolar gap Possible mixed acid-base disorder
Typical Causes of High Anion Gap
Alcohol-related ketoacidosis is a cause of high anion gap metabolic acidosis, but it is not the only one. A higher gap reflects the buildup of acid from several possible sources, and the differential diagnosis should remain open.
Notable causes include methanol poisoning, lactic acidosis, uremia, and diabetic ketoacidosis. Each condition can produce a similar laboratory pattern, though the history and accompanying findings often are different.
In toxic cases, toxic alcohol ingestion may also create a high anion gap and an osmolal gap, especially at first. That overlap is why careful interpretation matters. If toxic ingestion is suspected, urgent evaluation and toxin screening may be required.
Additional contributors may include renal failure, severe infection, shock, and other forms of metabolic acidosis. The anion gap calculator helps identify the abnormality, but the next step is identifying the underlying cause.
For clinical differential diagnosis, clinicians often compare patterns such as:
- Acid buildup driven by ketones in alcoholic ketoacidosis Severe hyperglycemia in diabetic ketoacidosis Increased lactate in lactic acidosis Retention of acids by the kidneys in uremia Potential osmolar gap shifts with methanol or other toxic alcohol ingestion
When It’s Time for Prompt Medical Attention
This condition can worsen rapidly, especially when it is combined with ongoing vomiting, dehydration, or impaired mental status. Symptoms may present with nausea and abdominal discomfort, then lead to weakness, tachycardia, and confusion.
Vomiting and fluid loss are especially concerning because they intensify volume depletion and can intensify the acid-base disturbance. A rapid heartbeat, or tachycardia, may signal significant physiologic stress or dehydration.
Confusion or disorientation is a major warning sign and should warrant urgent evaluation. This can reflect severe metabolic derangement, poor perfusion, hypoglycemia, toxic ingestion, or another medical emergency. If symptoms are severe or worsening, immediate medical care is needed.
Patients suspected of having alcoholic ketoacidosis should not rely on a calculator result alone. A high anion gap, low bicarbonate, ketonemia, or abnormal arterial blood gas can suggest a condition that needs urgent treatment, including fluids, glucose, electrolyte correction, and close monitoring.
Get urgent medical help if you notice:
- Persistent vomiting Severe dehydration Fast heart rate or weakness Confusion Concern for toxic alcohol ingestion Increasing acid-base imbalance
Frequently Asked Questions About Anion Gap Calculator and Alcoholic Ketoacidosis
What is an anion gap calculator used for in alcoholic ketoacidosis?
An anion gap calculator is designed to estimate the anion gap from routine lab values and help identify high anion gap metabolic acidosis. In alcoholic ketoacidosis, it can support the diagnosis when ketones, low bicarbonate, and other laboratory values suggest acid accumulation. It is most ethylene glycol high anion gap useful for clinical interpretation, not as a standalone diagnosis.
What formula is used to calculate the anion gap from sodium, chloride, and bicarbonate?
The standard anion gap formula is sodium - (chloride + bicarbonate). This uses measured serum chemistry values to estimate the amount of unmeasured anions in the blood. If the result is above the local reference range, it indicates an acid-base disturbance such as metabolic acidosis.
Why does alcoholic ketoacidosis to cause a high anion gap?
Alcoholic ketoacidosis causes a high anion gap because the body creates excess acidic ketones, especially beta-hydroxybutyrate. These acids increase ketonemia, lower bicarbonate, and contribute to high anion gap metabolic acidosis. Vomiting, poor intake, and volume depletion can worsen the metabolic derangement more pronounced.
Is albumin useful to correct the anion gap?
Yes, albumin should be considered because hypoalbuminemia can make the anion gap appear artificially low. An albumin-corrected anion gap can more clearly show the true acid-base status. This is especially important when interpreting labs in patients with malnutrition, long-term illness, or suspected alcoholic ketoacidosis.
Which other disorders can cause a high anion gap besides alcoholic ketoacidosis?
Other common causes include diabetic ketoacidosis, lactic acidosis, uremia, and toxic alcohol ingestion such as methanol. These conditions can share similarities in symptoms and laboratory findings, so the anion gap calculator should be used as part of a broader differential diagnosis and clinical evaluation.