What Is the Anion Gap?
The anion gap is a derived value that helps clinicians evaluate acid-base balance and recognize causes of metabolic acidosis. It derives from a routine electrolyte panel or serum chemistry test and is based on the relationship between serum sodium, serum chloride, and serum bicarbonate. In some formulas, potassium is included as well, though many modern calculations omit it because its contribution is usually small.
The anion gap shows the difference between measured cations and measured anions in the blood. It is especially useful because not all acids are directly measured. When acid builds up, the body may retain unmeasured anions, and the anion gap can help reveal that hidden metabolic derangement. This makes it an important part of diagnostic evaluation for patients with suspected acid accumulation.
Clinically, the anion gap is not a diagnosis by itself. Instead, it is a clue that supports the differential diagnosis. A normal or elevated value must always be interpreted in context with the patient’s laboratory values, symptoms, and overall clinical interpretation.
How the Anion Gap Calculator Works
An Anion Gap Calculator automates the anion gap formula so you can rapidly determine whether the result is high, normal, or adjusted by albumin. The most common formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some calculators add potassium:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
The calculator uses the input values for serum sodium, serum chloride, serum bicarbonate, and in some cases potassium to generate a result that can be compared with the reference interval. This anion gap in chronic kidney disease helps clinicians identify whether the blood chemistry suggests excess unmeasured acids or a different type of acid-base problem.
The calculation is straightforward, but the meaning is not. A elevated result can indicate extra acids in the bloodstream, while a normal result does not rule out acidosis. For this reason the calculator is most valuable when paired with the clinical picture, the electrolyte panel, and the rest of the serum chemistry results.
Many calculators also support a corrected anion gap when albumin is low. Because albumin is a negatively charged protein, low levels can make the anion gap appear falsely normal. Including this correction improves the accuracy of clinical interpretation, especially in patients with illness, inflammation, malnutrition, or liver disease.
How to Understand an Increased Anion Gap
An elevated result typically suggests high anion gap metabolic acidosis, which means acid has accumulated and increased the amount of unmeasured anions. This pattern often suggests a distinct source of acid production or decreased acid clearance.
Frequent causes include lactic acidosis, ketone-related acidosis, and kidney-related toxin buildup. In lactic acidosis, tissues produce excess lactate during low oxygen states, shock, or severe illness. Ketoacidosis occurs when ketone bodies accumulate, often in diabetes, starvation, or heavy alcohol use. Uremia develops when the kidneys cannot adequately remove acid and waste products, which is a regular issue in advanced kidney dysfunction.
High anion gap metabolic acidosis can also occur with poisoning or toxin exposure. Because the elevated gap shows unmeasured substances, the result can help refine the differential diagnosis. It does not determine the exact cause on its own, but it points toward disorders with acid retention or acid production.
When the result is elevated, it is useful to ask whether respiratory compensation is expected. The body often reacts to metabolic acidosis by increasing breathing to lower carbon dioxide. If the compensation does not fit the expected pattern, another acid-base disorder may also be present.
Typical Anion Gap Acidosis Pattern
Hyperchloremic metabolic acidosis is also called chloride-related acidosis. In this pattern, bicarbonate is depleted, but chloride goes up to maintain electroneutrality, so the calculated gap remains within the expected range. This explains why the anion gap can be normal even when metabolic acidosis is clearly present.
A classic cause is diarrhea, which results in loss of bicarbonate-rich intestinal fluid. Another important cause is renal tubular acidosis, where the kidneys cannot adequately acidify urine or reabsorb bicarbonate. In both situations, the problem is not excess unmeasured acids, but a change in measured electrolytes.
A normal anion gap state can be overlooked if the clinician focuses only on the gap number and not on the bicarbonate level or overall acid-base balance. If bicarbonate is low and chloride is high, the pattern may still suggest significant acidosis even when the calculated gap appears unremarkable.
Understanding this difference matters because the treatment and workup differ from those for high anion gap disorders. A careful review of the serum bicarbonate, chloride, and kidney function helps separate hyperchloremic acidosis from acid accumulation due to unmeasured anions.
Adjusting the Anion Gap for Albumin
Albumin is among of the main determinants of the anion gap because it bears a negative charge and contributes to normal plasma electroneutrality. When albumin is low, the measured anion gap may be falsely normal. This is why a corrected anion gap is often favored in patients with hypoalbuminemia.
The correction takes into account the effect of reduced protein binding and the loss of albumin’s negative charge. In practical terms, low albumin can hide a high anion gap metabolic acidosis by making the gap look less elevated than it truly is. Using a correction factor improves the diagnostic value of the result.
A common approach is to add a fixed amount to the calculated gap for every decrease in albumin below normal. The exact method may change by institution, but the purpose is the same: adjust the number so it better reflects the real burden of unmeasured anions. This is especially important in unstable patients, where hypoalbuminemia is common and metabolic derangement may be profound.
When interpreting a corrected value, remember that albumin influences the buffer system and the measured gap indirectly. A low uncorrected result should not be relieving if the patient is ill and the albumin is reduced. The corrected anion gap can expose hidden high anion gap metabolic acidosis that would otherwise be missed.
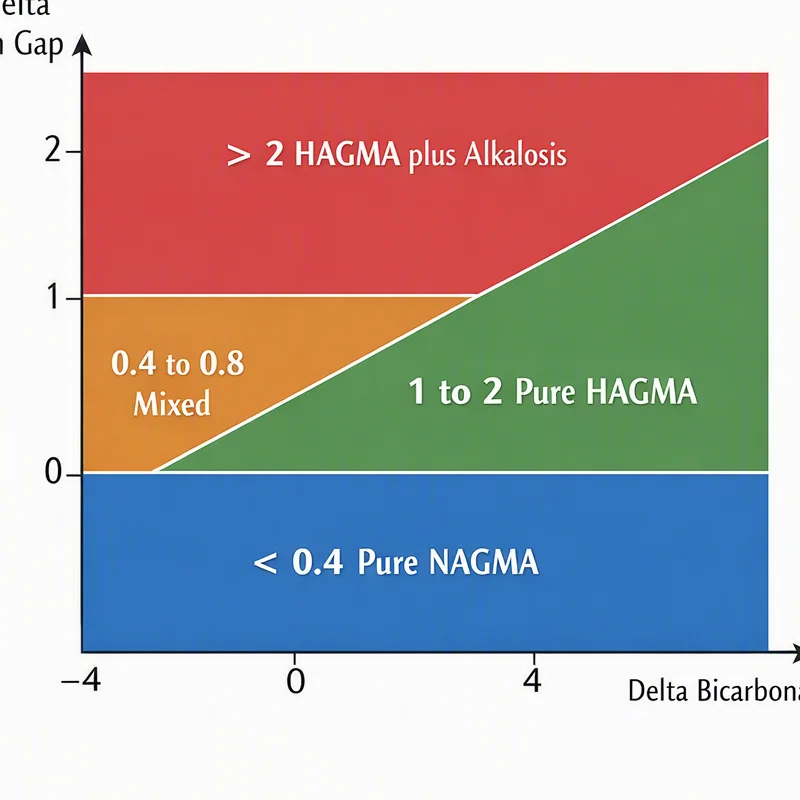
Applying the delta gap to Detect mixed acid-base disorders
The delta-gap and delta ratio support spot a mixed acid-base disorder when elevated anion gap metabolic acidosis is detected. These tools relate the increase in the anion gap to the fall in bicarbonate, offering insight into whether another disorder is occurring at the same time.
The idea is easy to follow: if the anion gap has increased more than expected relative to the drop in bicarbonate, there may be an additional metabolic alkalosis. If the bicarbonate has fallen more than expected, there may be an additional normal anion gap metabolic acidosis. The delta ratio helps quantify this relationship.
For example, if the anion gap is elevated but bicarbonate is not as low as expected, metabolic alkalosis may be masking part of the acid load. This can happen with vomiting, diuretic use, or other concurrent conditions. Conversely, a very low bicarbonate with only a modest rise in the gap may suggest that more than one acid-base disorder is present.
Using the delta gap is especially valuable in complex diagnostic evaluation. It adds nuance beyond the initial Anion Gap Calculator result and helps explain why some patients do not fit a single textbook pattern.
Main Causes of Metabolic Acidosis
The causes of metabolic acidosis are often grouped by whether the anion gap is elevated or within normal limits. This framework enhances differential diagnosis and aids in finding the underlying process quickly.
Important causes of high anion gap metabolic acidosis include toxic alcohols, salicylate poisoning, sepsis, lactic acidosis, ketoacidosis, and uremia. Toxic alcohols can produce acidic metabolites that increase the gap. Salicylate poisoning may lead to a complex acid-base picture, at times with respiratory alkalosis and metabolic acidosis together. Sepsis can result in poor tissue perfusion and lactic acidosis. Chronic kidney disease can progress to uremia, reducing acid clearance and allowing acids to accumulate.
Normal anion gap metabolic acidosis is often the result of diarrhea or renal tubular acidosis, but it can also appear after large-volume saline administration or in other contexts where chloride increases as bicarbonate falls. The key point is that both categories reflect metabolic acidosis; the anion gap simply helps separate the mechanism.
In practice, clinicians use the gap together with symptoms, medication history, kidney function, and other laboratory values to build a more complete picture. That broader view is often more helpful than any single number.
Limitations of the Anion Gap Calculation
Even though the anion gap is valuable, it has significant limitations. Analytical variation can influence the result because different analyzers and methods may yield slightly different electrolyte values. This means the reference range may differ across hospitals.
Measurement error can also affect the calculation. Even small variations in sodium, chloride, or bicarbonate can modify the final number. Since the anion gap is computed rather than directly measured, it inherits any inaccuracy present in the underlying lab tests.
Another limitation is that the gap does not identify the exact acid involved. A high value may result from lactate, ketones, toxic substances, or retained acids from kidney failure, but the calculator itself cannot differentiate among them. That is why clinical correlation matters.
The osmolar gap is a connected but separate tool that can help evaluate suspected toxic alcohol exposure. It reflects unmeasured osmoles rather than unmeasured anions. In some poisoning cases, both the osmolar gap and anion gap may be abnormal, but one does not take the place of the other.
For these reasons, the Anion Gap Calculator should be regarded as part of a broader diagnostic evaluation rather than a standalone answer.
When to Seek Urgent Medical Evaluation
Specific cases of metabolic acidosis require urgent attention. Profound acidosis can impair organ function and lead to worsening instability if not treated promptly. This is especially concerning when the cause is fast-moving, such as sepsis, poisoning, or severe kidney failure.
Mental status changes is a major warning sign. Confusion, drowsiness, agitation, or reduced responsiveness can reflect severe metabolic derangement or a dangerous underlying cause. These symptoms should not be ignored, especially if they occur alongside abnormal laboratory values.
Watch for signs that respiratory compensation is becoming inadequate. Rapid breathing may initially help correct the acid-base problem, but if breathing becomes exhausted or inadequate, carbon dioxide can rise and the condition can worsen. This is an emergency.
Also note to pay attention to electrolyte abnormalities, such as serious changes in potassium, sodium, or bicarbonate. Such disturbances can affect the heart, muscles, and nervous system. When metabolic acidosis comes with notable symptoms, it should be evaluated promptly by a clinician.
To put it simply, an abnormal result from an Anion Gap Calculator is not something to panic over by itself, but it should be taken seriously when paired with symptoms, worsening illness, or abnormal vital signs.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the anion gap from routine electrolyte values and support the evaluation of metabolic acidosis. It assists with clinical interpretation by highlighting which lab reference for anion gap whether the pattern suggests high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or a possible mixed acid-base disorder.
What is considered a normal anion gap in metabolic acidosis?
A normal anion gap is a result that falls within the laboratory’s reference interval. Because ranges vary by method and lab, the exact number can differ. In metabolic acidosis, a normal gap often points toward hyperchloremic acidosis, such as diarrhea or renal tubular acidosis, rather than acid accumulation from unmeasured anions.
How do you correct the anion gap for low albumin?
To correct the anion gap for low albumin, clinicians use a correction factor that adjusts the measured value upward when hypoalbuminemia is present. This accounts for the fact that albumin normally contributes negative charge through protein binding. The corrected anion gap can reveal hidden high anion gap metabolic acidosis that the uncorrected number may miss.
What causes a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, uremia, toxic alcohols, and salicylate poisoning. Sepsis and chronic kidney disease are also important contributors because they can lead to acid accumulation or impaired acid clearance.
Can a typical anion gap also mean a metabolic acid buildup?
Yes. A typical anion gap can indeed occur with metabolic acid buildup, especially in normal anion gap metabolic acidosis or elevated-chloride acidosis. Disorders such as diarrhea and renal tubular acidosis can reduce bicarbonate while chloride goes up, leaving the gap in normal range even though acidosis is occurring.