What Is the anion gap?
The anion gap is an calculated measure used to assess acid-base balance by comparing major measured ions in a serum chemistry or electrolyte panel. An Anion Gap Calculator helps doctors and students quickly estimate whether there is an abnormal amount of hidden acids in the blood. At its core, the calculation uses serum sodium, serum chloride, and serum bicarbonate to assess the relationship between cations and anions.
The basic idea is simple: the body keeps electrical neutrality, so the positive and negative charges in blood must offset each other. Because not every https://anion-gap-guide071.yousher.com/anion-gap-calculator-for-acid-base-balance-interpretation ion is directly measured, the anion concentration is inferred from routine laboratory values. A shift in this balance can point toward a metabolic abnormality, especially metabolic acidosis. In clinical practice, the anion gap is a fast clinical tool for narrowing the cause of an acid-base disorder.
Most providers review the anion gap alongside the chloride level, sodium level, and bicarbonate level, then interpret the result in the context of symptoms, medications, and blood gas findings. That broader interpretation matters because the anion gap alone does not tell the full story. It is one piece of blood gas interpretation and should be considered with respiratory compensation and the patient’s overall condition.
How the Anion Gap Calculator Operates
The traditional anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)This calculation estimates the amount of unaccounted-for anions in the body. When sodium is compared with chloride and bicarbonate, the resulting gap reflects substances such as proteins, phosphates, sulfates, lactate, and ketones that are not listed directly in the basic panel.
A standard reference range differs by laboratory because methods and instruments differ. That is why clinicians should always interpret the number using the local reference interval rather than relying on a single universal cutoff. The specific reporting method also affects whether potassium is included; most modern calculators omit it for simplicity and consistency.
Many modern calculators also support albumin correction. Albumin is a negatively charged protein and is a major unmeasured anion. If albumin is low, the measured anion gap may appear falsely normal. A corrected anion gap adjusts for this by applying a correction factor based on the albumin level, improving clinical accuracy in patients with low protein states.
The result of the calculator is not just a number. It is a first clue for deciding whether the patient likely has high anion gap metabolic acidosis, another type of acid-base disorder, or a mixed pattern. The best interpretation comes from combining the anion gap with bicarbonate level, pH, and the rest of the serum chemistry.
What Is Delta-Delta Analysis?
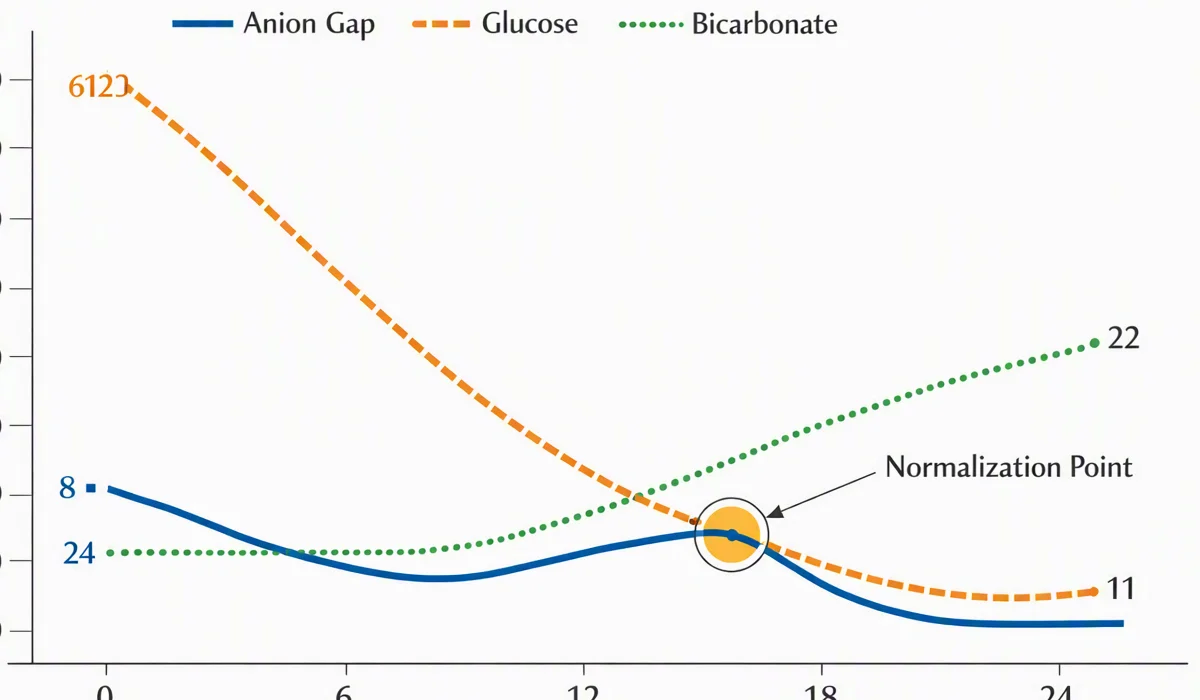
Delta delta analysis is used to determine whether a patient with a high anion gap also has an additional acid-base disturbance. This approach compares the change in the anion gap to the change in bicarbonate. It helps reveal a mixed acid-base disorder rather than thinking that all abnormalities are explained by a single process.
In a typical case of metabolic acidosis with elevated anions, the extra acid consumes bicarbonate in roughly equal proportion to the rise in unmeasured anions. If the bicarbonate has fallen more than expected, there may be a second process such as normal anion gap metabolic acidosis. If the bicarbonate has fallen less than expected, a concurrent alkalinizing disturbance such as metabolic alkalosis may be present.
This is where delta gap and delta ratio become valuable. The delta gap compares the increase in anion gap to the decrease in bicarbonate. The delta ratio shows that relationship numerically, giving an efficient way to screen for mixed disorders. In practical terms, delta delta helps answer a key question: is the patient’s acid-base pattern explained by a single disturbance, or is more than one problem occurring at once?
Blood gas data often adds important context. Blood gas interpretation can show whether respiratory compensation is adequate, inadequate, or excessive. That matters because a patient with metabolic acidosis may also have a respiratory issue affecting pH, which changes the overall picture.
How to Interpret Delta-Delta Results
When interpreting delta delta properly, begin by determining whether the patient has a elevated anion gap process. Then compare the rise in gap with the drop in bicarbonate. The simplest clinical pattern uses the concept of expected bicarbonate. If the bicarbonate is close to what would be predicted from the elevation in anion gap, the disturbance may be a pure high anion gap metabolic acidosis. If not, a different process should be considered.
Here is the approach used in many bedside assessments:
- If the delta gap is near zero, the relationship between anion gap and bicarbonate is aligned. If bicarbonate is below the expected bicarbonate, suspect an added normal anion gap metabolic acidosis. If bicarbonate is greater than expected, consider concurrent metabolic alkalosis or chronic compensation.
In practice, the delta ratio is often used as a rapid method. A low ratio suggests that bicarbonate has fallen more than expected for the degree of gap elevation, which suggests a mixed picture with non-gap acidosis. A high ratio suggests smaller bicarbonate loss than expected, which may indicate alkalosis layered on top of a high-gap process.
These findings are especially important because a patient can have normal anion gap metabolic acidosis and high anion gap metabolic acidosis at the same time. The result may seem less dramatic on a single lab printout, yet the underlying acid-base disorder is more complex. Delta delta clarifies the interpretation and improves clinical decision-making.
Stepwise Sample Calculation
Presented below is a sample calculation that demonstrates how an Anion Gap Calculator and delta ratio analysis can be used together.
Step 1: Examine the laboratory results. Assume the patient has:
- Sodium: 140 Chloride: 100 Bicarbonate level: 14 Albumin: low enough to require correction
Step 2: Determine the anion gap. With the anion gap formula:
140 − (100 + 14) = 26This is elevated and suggests a high anion gap metabolic acidosis.
Step 3: Use albumin correction. If albumin is reduced, the measured gap may not fully reflect the true abnormality. After albumin correction, the corrected anion gap may be even higher. This adjustment is especially helpful when the clinical picture suggests a significant metabolic disturbance but the raw anion gap is only slightly abnormal.
Step 4: Calculate the delta anion gap. If the normal baseline gap is 12, the delta anion gap is 26 − 12 = 14.
Step 5: Compare that with bicarbonate loss. If normal bicarbonate is 24, the bicarbonate drop is 24 − 14 = 10.
Step 6: Work out the delta ratio. Delta ratio = 14 / 10 = 1.4.
Clinical interpretation: A ratio around this range often fits a straightforward high-gap metabolic acidosis, without a strong signal for a second major process. However, if the bicarbonate had been much lower than expected, that would suggest an added normal anion gap metabolic acidosis. If the bicarbonate had stayed higher than expected, a concurrent alkalosis would be considered.
In this way, the sample calculation shows more than a number. It links the corrected anion gap, delta anion gap, and serum bicarbonate into a useful clinical picture. That is the real value of the calculator: it supports a more nuanced diagnosis rather than a single-label answer.
Frequent Causes of an Elevated Anion Gap
Various conditions may produce an higher gap by adding to unmeasured acids in the bloodstream. The leading causes are:
- Lactic acidosis, often associated with poor tissue perfusion, severe illness, or increased lactate production Ketoacidosis, that can arise with diabetes, starvation, or alcohol-related states Renal failure, in which acid retention and reduced excretion of unmeasured acids elevate the gap Toxic alcohol ingestion, including substances that generate acid metabolites and profoundly disturb serum chemistry
These disorders are commonly placed among high-gap states because they produce a form of metabolic acidosis with accumulation of acids that are not reflected directly in standard lab measurements. A careful review of the history, medication list, and blood gas interpretation is essential to separate these causes.
For example, ketoacidosis may present with elevated ketones and profound bicarbonate loss. Lactic acidosis may be seen when the body is under stress and oxygen delivery is impaired. Renal failure can produce progressive acid retention, and toxic alcohol ingestion should always be considered when the clinical setting is suspicious and the acid-base pattern is severe or unexplained.
Limitations plus Patient Care Warnings
While an Anion Gap Calculator is useful, it cannot fully substitute for medical assessment. Multiple factors influence the result and must be considered during interpretation.
To begin with, albumin correction is crucial because low albumin can hide an elevated gap. Lacking that adjustment, a patient with substantial acid accumulation may seem to have a normal value. Second, lab variation can alter the reference interval from one instrument to another, so consistently read the number using the local report. Finally, electrolyte abnormalities can distort the apparent balance between sodium, chloride, and bicarbonate, notably in medically complex hospitalized patients.
The anion gap also captures only one part of acid-base balance. A patient can have a near-normal gap and still have a significant disorder. Likewise, respiratory processes can affect pH even when the metabolic component is only somewhat abnormal. That is why the calculator should be used together with blood gas interpretation, symptom review, and other laboratory values.
It is also worth remembering that a single snapshot does not always show the whole story. Trends in serum sodium, serum chloride, and serum bicarbonate may be more revealing than one isolated draw. In clinical practice, the best use of this tool is to support recognizing patterns, not to replace broader diagnostic reasoning.
FAQ
What does an Anion Gap Calculator measure?
An anion gap calculator determines the difference between measured cations and negative ions, usually using serum sodium, serum chloride, and serum bicarbonate. It estimates the level of unmeasured anions and helps detect metabolic acidosis and related acid-base disorders.
How do you calculate delta delta for anion gap interpretation?
Delta delta evaluates the rise in the anion gap to the fall in bicarbonate. Start by subtracting the normal anion gap from the measured value to get the delta anion gap, then match that number with the drop in bicarbonate from normal. The result helps show whether there is a mixed disorder.
When should albumin correction be used?
Albumin correction should be used when serum albumin is low, because albumin is a major unmeasured anion. Without correction, the corrected anion gap may be too low and a clinically important high-gap state may be missed.
What does an elevated delta delta ratio suggest?
A high delta ratio usually means the rise in anion gap is greater than the fall in bicarbonate, which can suggest concurrent metabolic alkalosis or another process that is offsetting the expected bicarbonate loss. It is a clue that the patient may have a mixed acid-base disorder.
Is a normal anion gap still possible in a mixed acid-base disorder?
Yes. A patient may have a normal measured gap and still have a mixed acid-base disorder, especially if one process raises the gap while another lowers it, or if the gap is masked by hypoalbuminemia. That is why blood gas interpretation, albumin correction, and the full clinical context matter.