What the Anion Gap Assesses
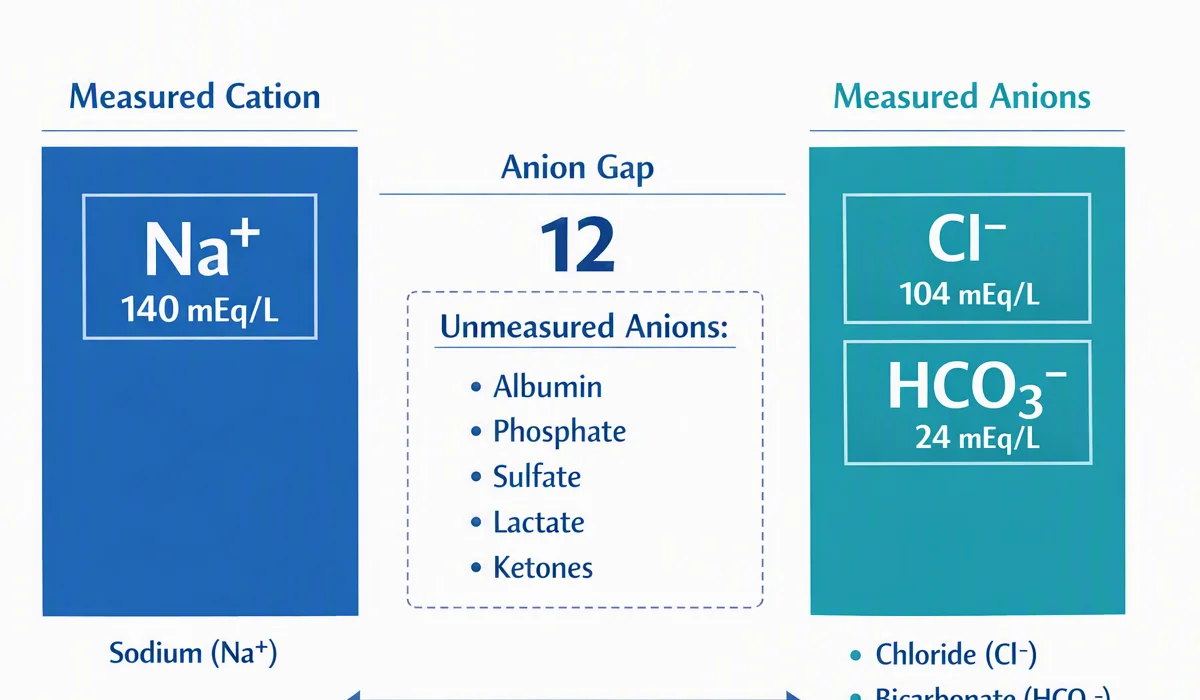
The anion gap is a helpful part of acid-base evaluation because it helps clinicians and students understand how the key electrolytes connect to one another in the blood. It is not a simple measurement of a one substance. Instead, it is a calculated value derived from common serum chemistry tests that shows the balance between measured cations and measured anions.
In clinical terms, the anion gap assists in identify whether a patient has an acid-base disorder, especially metabolic acidosis. When the body accumulates acids or reduces bicarbonate, the chemistry panel changes in predictable ways. An elevated or unexpected gap can point toward hidden acids, also called unmeasured anions, that are not directly listed on a standard electrolyte panel.
The most relevant measured values in this calculation are sodium, chloride, and bicarbonate. Some formulas also include potassium, though many clinical settings omit it for simplicity. Because the result is derived from standard serum electrolytes and other blood chemistry data, the anion gap serves as a fast diagnostic tool during patient assessment.
An Anion Gap Calculator makes it more convenient to calculate anion gap values rapidly and consistently. That can support a clearer understanding of the cause of acidosis, whether the issue is a simple bicarbonate loss, an excess acid load, or another process affecting the body’s acid-base balance.
How to Work With the Anion Gap Calculator
To work with an Anion Gap Calculator, input the serum values for sodium, chloride, and bicarbonate from the lab report. These values are usually listed in milliequivalents per liter, and the calculator uses the standard formula to calculate the result.
Most calculator tools are designed for rapid bedside review or educational use. They allow convert a basic blood chemistry panel into a more meaningful metabolic acidosis evaluation. If you also have the albumin level available, a more advanced calculator may enable you to correct for albumin and produce a corrected anion gap.
Here is the basic process:
- Input the sodium value from the lab report. Input chloride and bicarbonate values from the same sample if possible. As an option: add potassium if the calculator includes it. If needed: add albumin if you want a corrected value. Review the result against the expected reference range or normal range.
For reliable interpretation, the numbers should come from the same blood draw whenever possible. Changes in timing, fluid status, or treatment can affect the result. The calculator is most useful when paired with the rest of the clinical picture rather than used as a standalone answer.
Anion Gap Equation and Computing Stages
The standard anion gap formula is:
Na minus Cl minus HCO3
In expanded form, the formula becomes:
Anion gap = sodium - chloride - bicarbonate
Some providers include potassium in the equation:
Anion gap = sodium + potassium - chloride - bicarbonate
This method may produce a somewhat higher result, but both approaches are used in practice. What matters is to know which method the calculator is using so the interpretation matches the calculation.
To determine the value step by step:
- Start with the sodium value. Deduct chloride. Subtract bicarbonate. If potassium is included, enter potassium before subtracting chloride and bicarbonate.
Calculation example: With sodium at 140, chloride equals 102, and bicarbonate comes to 24, the calculation would be 140 - 102 - 24 = 14. With potassium added at 4, then 140 + 4 - 102 - 24 = 18.
This basic math can help identify an high anion gap, but interpretation depends on the lab’s techniques and the patient’s overall condition. A result that seems abnormal should always be considered in the setting of symptoms, medications, and other lab results.
Typical Anion Gap Compared with High Anion Gap
A anion gap in the normal range usually indicates that the equilibrium between measured cations and anions is in the expected expected range. That does not automatically imply the patient is normal, but it may indicate that the acidosis, if present, is due to bicarbonate loss rather than accumulation of unmeasured acids.
A high anion gap is more concerning because it often suggests the presence of extra acids in the bloodstream. This pattern is classically seen in high anion gap metabolic acidosis, where acids accumulate and bicarbonate falls as the body tries to counteract the acid load.
Recognizing the difference is central to metabolic acidosis workup. A normal gap can be associated with diarrhea, renal tubular issues, or bicarbonate loss. A high gap more often suggests hidden acid accumulation from conditions such as lactic acidosis, ketoacidosis, or kidney-related causes.
The anion gap is not a diagnosis by itself. It is a clue. The result should inform additional testing and support broader clinical reasoning rather than take the place of it.
Adjusted Anion Gap & Albumin Adjustment
Albumin is a significant hidden anion in blood, so low albumin can make the measured gap look reduced than it really is. This is why many of the clinicians use a corrected anion gap when hypoalbuminemia is present.
If albumin is low, the usual gap may miss the severity of an acid-base problem. In that situation, the calculator may correct for albumin to more clearly reflect the underlying chemistry. This adjustment is especially useful when interpreting lab results in severely ill patients or anyone with low protein levels.
Why does this matter? A patient can appear to have a standard anion gap even when excess acids are present if albumin is low enough. The corrected result can reveal a hidden high anion gap that would otherwise be missed.
Albumin adjustment improves clinical interpretation because it accounts for one of the most important contributors to the body’s electrical balance. In practice, corrected values are often more useful than the raw number alone, especially when evaluating potential acid-base disturbances.
Frequent Causes of a Raised Anion Gap
An raised anion gap typically suggests that the body has accumulated acids or other unmeasured charged substances. Several conditions are traditionally associated with this pattern, and identifying them helps pinpoint the reason for acidosis.
Lactic acid buildup is a leading cause. It occurs when lactate builds up due to reduced oxygen supply, shock, severe illness, or other stressed conditions. Because lactate is an unmeasured anion, it drives the gap higher.
Acid buildup from ketones is another key cause. This may occur in diabetes, starvation, or alcohol-related states, where ketone bodies collect and disrupt the acid-base balance.
Uremic buildup from reduced kidney function is also important. In severe Additional reading kidney failure, acids are not cleared effectively, and retained toxins lead to a higher gap.
Other causes can include toxins, medications, and metabolic conditions that increase acid production or decrease acid clearance. The main point is that a high gap should prompt a search for hidden acid generation or poor clearance rather than a narrow focus on the number itself.
How to Understand Results in Medical Context
Reading the anion gap correctly requires more than a number. A good clinical interpretation blends the gap with signs, vitals, history, medications, and other lab values such as an arterial blood gas.
The arterial blood gas helps determine whether the patient actually has acidosis or alkalemia, whether compensation is occurring, and whether the primary disorder aligns with the chemistry panel. The anion gap then brings another layer by identifying whether the metabolic problem is likely due to extra acids or bicarbonate loss.
The delta gap is also useful in more complex cases. It contrasts the change in the anion gap with the change in bicarbonate to look for mixed disorders. For example, a patient may have high gap metabolic acidosis along with a separate metabolic alkalosis or a concurrent normal gap acidosis.
This is why the Anion Gap Calculator is best considered as part of a broader workflow. It assists with decision-making, but the final interpretation should combine the complete acid-base picture, including the patient’s clinical status and any possible base deficit.
Limitations of Anion Gap Calculation
Although the anion gap is important, it has several limitations. One issue is lab variation. Different instruments, assay methods, and reporting practices can yield slightly different results, which means the reference range may vary by laboratory.
Another limitation is that the gap only captures measured and unmeasured anions indirectly. It does not identify the specific acid responsible. A high value may suggest a disorder, but it cannot distinguish between lactic acidosis, ketoacidosis, or other causes without additional context.
Electrolyte measurement problems can also affect accuracy. Severe electrolyte disorders, changes in protein concentration, or unusual blood chemistry patterns may distort the result. In addition, the presence of certain ions can change how the gap appears even if the true acid burden has not changed dramatically.
Given these limitations, the anion gap should be used as a segment of a thorough acid-base disorder review. It remains a valuable indicator, but not a final answer. The best use of the calculator is to aid thoughtful interpretation of lab results, not to take the place of clinical reasoning.
FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An Anion Gap Calculator is used to compute anion gap values from routine lab results and help with acid-base evaluation. It is especially valuable in metabolic acidosis evaluation because it can assist in identifying whether the problem is related to hidden acids, bicarbonate loss, or another acid-base disorder.
What is the normal anion gap range?
The reference range for the normal anion gap varies by laboratory and by whether potassium is included in the formula. In general, many labs classify a value in the low to mid-teens to be normal, but the exact range should always be assessed using the reporting lab’s stated normal range.
How do you calculate the anion gap from lab values?
Use the standard anion gap formula: sodium - chloride - bicarbonate. Some versions include potassium before subtracting chloride and bicarbonate. The calculator performs this step automatically using the provided serum electrolytes, making it easier to assess blood chemistry results quickly.
Why do you correct the anion gap for albumin?
You correct for albumin because low albumin can obscure a true gap elevation. In hypoalbuminemia, the measured value may appear normal even when unmeasured acids are present. A corrected anion gap gives a more reliable picture of the patient’s acid-base status.
What conditions cause a high anion gap?
Common causes of a high anion gap include lactic acidosis, ketoacidosis, and uremia. Severe renal failure, toxins, and other causes of retained acids can also produce an elevated value. The result should always be interpreted in the context of the full clinical picture and any associated arterial blood gas findings.