How to Understand the Anion Gap?
The anion gap is a useful way to evaluate the distribution of electrically charged particles in the blood. It is a computed value that helps identify an acid-base imbalance, especially when there are unmeasured anions contributing to a metabolic derangement. In plain language, it examines the main measured cations and anions in serum chemistry, usually using sodium, chloride, and bicarbonate.
A standard formula is:
Anion gap = sodium - (chloride + bicarbonate)
This formula is often obtained from a basic metabolic panel. The result can point to hidden causes of acid-base imbalance, including high anion gap metabolic acidosis. When the anion gap is elevated, it often means there are more acids in the bloodstream that are not directly measured in the routine lab panel.
The anion gap is not a diagnosis by itself. It is a clinical clue that must be interpreted in the context of symptoms, the clinical assessment, and other lab data. Things such as albumin, electrolyte imbalance, and changes in chloride can all influence the result. Because albumin is one of the main unmeasured anions, a low albumin level can make the anion gap appear reduced than it really is.
How to Use an Anion Gap Calculator
An Anion Gap Calculator is a helpful tool for quickly estimating the gap from standard labs. You typically enter the values for sodium, chloride, and serum bicarbonate from the basic metabolic panel. The calculator then follows the standard formula and gives you a number that can aid lab interpretation.
To use the result well, it helps to look past the single number. A normal anion gap does not always eliminate a serious problem, and an elevated anion gap does not reveal the exact cause. The calculator is most helpful when paired with clinical context, a symptom pattern, and a broader toxicology workup if poisoning is possible.
Albumin correction is especially important. Because albumin affects the measured balance of electrolytes, a low albumin level can mask an elevated anion gap. Correcting for albumin may uncover hidden acidosis and improve acid-base balance interpretation. In many cases, the corrected value provides a more reliable picture of the underlying metabolic derangement.
Serum bicarbonate is a key input because it reflects the body’s buffering status. A low bicarbonate level often points toward metabolic acidosis, while a higher value may be seen in other settings. When the number is abnormal, it should lead to a search for the reason, not just the result.
Can Salicylates Increase the Anion Gap?
Absolutely. Salicylates can elevate the anion gap, most notably in salicylate toxicity. Aspirin is the most familiar salicylate, and overdose or repeated excess use can produce a classic toxicology picture. One major effect is elevated anion gap metabolic acidosis caused by the accumulation of unmeasured anions and organic acids.
Salicylates interfere with cellular metabolism, raise acid production, and disturb normal respiratory and metabolic control. This creates a complicated acid-base disorder rather than a simple one. A person can have both respiratory alkalosis and metabolic acidosis at the same time, which is why salicylate poisoning is a well-known mixed disorder.
The anion gap may increase because of multiple contributing factors, including lactate production and the presence of ketones. Salicylates can also impair oxidative metabolism and promote a metabolic state where acids accumulate faster than the body can compensate. That is why the elevated anion gap is an important diagnostic clue when aspirin exposure or salicylates are suspected.
However, salicylate toxicity does not always appear with the same lab pattern at every stage. Early on, the anion gap may be normal, particularly before a major acid load builds up or before lab changes fully evolve. Later, as metabolic acidosis deepens, the gap is more likely to increase.
Why Salicylate Poisoning Can Cause Mixed Acid-Base Disorders
Salicylate poisoning can cause a mixed disorder because it affects both breathing and metabolism. Early in toxicity, respiratory alkalosis is common because salicylates stimulate the respiratory center, causing hyperventilation. This reduces carbon dioxide and can elevate the blood pH initially.
At the same time, salicylates increase metabolic acid generation and interfere with normal energy use, leading to metabolic acidosis. That acidosis can be driven in part by lactate and ketones, especially when the body shifts into a stressed, inefficient metabolic state. The result is a compensatory response that can look confusing on labs: an alkaline pH from hyperventilation, but a low bicarbonate level from acid accumulation.
This explains why salicylate toxicity is a well-known example of a mixed disorder. The patient may look like they have one problem on the arterial blood gas, yet the blood chemistry suggests another. Detailed acid-base balance review is essential, especially when the clinical picture includes poisoning or overdose symptoms.
Common Laboratory Findings in Salicylate Overdose
When salicylate overdose is suspected, the arterial blood gas is often one of the best tests. It can show respiratory alkalosis, acidic metabolic changes, or a mixed picture depending on the phase of illness. The pH may be alkaline, normal, or acidic, so looking only at pH can overlook the diagnosis.
The bicarbonate level is usually low when metabolic acidosis is present. The serum salicylate level is also essential for toxicology assessment, but it should be interpreted alongside symptoms and acid-base findings rather than in isolation. A person with severe symptoms may need repeated testing anion gap in chronic kidney disease because levels and clinical status do not always match perfectly at a single time point.
Other frequent findings may include abnormal electrolytes, changes in chloride, and evidence of respiratory compensation. The basic metabolic panel can show a reduced bicarbonate level and an elevated anion gap, which strengthens the suspicion for salicylate poisoning. In severe cases, the lab pattern may indicate widespread metabolic derangement rather than a single isolated abnormality.
When the Anion Gap May Be Normal or Elevated
In salicylate toxicity, the anion gap may renal disease anion gap implications be unchanged early and raised later. That variation depends on the timing, severity, and whether albumin is low enough to mask the true gap. Because albumin is an important unmeasured anion, hypoalbuminemia can make laboratory interpretation more difficult.
When albumin is low, an albumin correction should be considered so the anion gap is not falsely reassuring. This matters because the body may already be experiencing metabolic acidosis even if the uncorrected number looks borderline. In other words, the normal anion gap is not always truly normal when albumin is reduced.
The key is to interpret the result as part of the full clinical assessment. The presence of unmeasured anions, changes in bicarbonate, and the symptom pattern can all reinforce the diagnosis. A calculator result is only one piece of the toxicology puzzle.
Other Sources of an Increased Anion Gap to Exclude
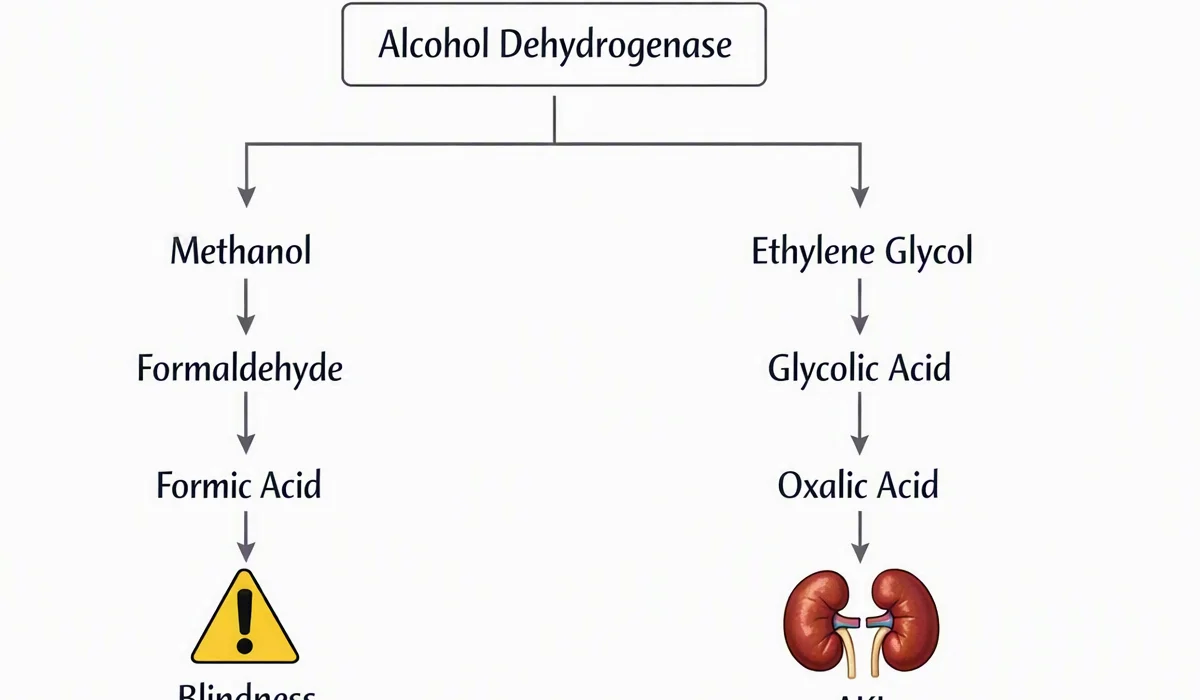
Not all elevated anion gap is the result of salicylates. A careful differential diagnosis is essential because several dangerous conditions can produce a matching lab pattern. Common alternatives include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols.
Lactic acidosis can occur with impaired tissue perfusion, severe infection, or additional metabolic stress. Ketoacidosis may be seen in diabetes, starvation, or prolonged vomiting, and it often produces ketones that elevate the gap. Renal failure can cause acid retention because the kidneys cannot eliminate acids effectively. Toxic alcohols are another major concern because they can create serious acid-base abnormalities and require urgent treatment.
This is why lab interpretation must go beyond a single Anion Gap Calculator value. The result should be matched with the history, symptoms, serum chemistry, and, when needed, additional toxicology tests. The pattern of acid-base disorder can help limit the cause, but it seldom tells the whole story by itself.
When to Seek Prompt Medical Evaluation
Immediate medical assessment is essential if salicylate toxicity is possible, especially when overdose indications are present. Warning signs can include tinnitus, hyperventilation, vomiting, confusion, fever, or rapid worsening of overall condition. Tinnitus is a classic symptom and should not be ignored when aspirin or other salicylates are involved.
As salicylate poisoning can worsen rapidly, poison control should be contacted right away if an overdose is suspected. This is especially important if the person is breathing rapidly, has an altered mental status, or shows signs of metabolic acidosis. Prompt treatment decisions depend on the clinical picture, not just the lab number.
If a person has taken more than the recommended amount of aspirin or another salicylate product, do not wait for the symptoms to worsen. Quick assessment can help confirm the diagnosis, measure the serum salicylate level, and evaluate acid-base balance before the situation becomes more severe.
Frequently Asked Questions
Will salicylates always increase the anion gap?
No. Salicylates may not always increase the anion gap right away. At the start of salicylate toxicity, the gap may still be normal, especially before significant metabolic acidosis develops or if albumin is low enough to mask the rise. Over time, however, salicylates often lead to an elevated anion gap because of accumulating unmeasured anions and acid generation.
Does aspirin toxicity cause both respiratory alkalosis and metabolic acidosis?
Yes, it can. Aspirin toxicity is a classic cause of a mixed disorder with both respiratory alkalosis and metabolic acidosis. Salicylates stimulate breathing, which lowers carbon dioxide, while also driving acid accumulation that lowers bicarbonate. That combination can make the arterial blood gas and serum chemistry look conflicting unless they are interpreted together.
What anion gap result is concerning for salicylate poisoning?
There is no single cutoff that proves salicylate poisoning, but an elevated anion gap with low bicarbonate and compatible symptoms should raise concern. The exact number matters less than the pattern and the clinical context. If the patient has hyperventilation, tinnitus, or other overdose symptoms, further toxicology evaluation is warranted even if the gap is only mildly abnormal.
Must albumin be corrected when interpreting the anion gap?
Yes. Albumin correction is often important because low albumin can make the anion gap appear falsely normal or less abnormal than it really is. Since albumin is a major unmeasured anion, correcting for it improves clinical interpretation and helps identify hidden metabolic acidosis. This is especially useful when the basic metabolic panel seems inconsistent with the patient’s symptoms.
What other conditions can look similar to salicylate toxicity on labs?
Several conditions can resemble salicylate toxicity on labs, including lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each can produce an elevated anion gap and metabolic acidosis, so the diagnosis depends on the overall symptom pattern, history, and additional testing. An arterial blood gas, serum salicylate level, and careful acid-base balance review help separate these possibilities.