Interpreting the anion gap is one of the most practical steps in reviewing an acid-based state. An Anion Gap Calculator can simplify the math, but clinical interpretation still depends on the overall pattern of lab values, symptoms, and the acid-base picture. In ketoacidosis, the anion gap helps show whether unmeasured anions are accumulating because of ketone production, whether the problem is truly metabolic acidosis, and anion gap in chronic kidney disease whether treatment is effective.
This guide guides you through the lab logic step by step so you can interpret the diagnostic pattern with more confidence. It also describes how albumin changes the result, why beta-hydroxybutyrate matters, and how to tell ketoacidosis apart from other causes of high anion gap metabolic acidosis.
What Means
This anion gap serves as a computed value derived from the main ions in a serum chemistry or electrolyte panel. It measures the disparity between measured cations and measured anions, aiding identify unmeasured anions in the blood. The classic calculation uses serum sodium, serum chloride, and serum bicarbonate.
The basic idea is simple: serum sodium represents the major measured positive charge, while serum chloride and serum bicarbonate represent the major measured negative charges. When the gap increases, it often means additional acids or unmeasured anions are present. That makes the anion gap a important part of acid-base interpretation, especially when you are trying to confirm metabolic acidosis.
In practice, the anion gap is a lens into the body’s acid-base balance. A normal value does not guarantee normal physiology, but a high value strongly suggests a metabolic derangement involving unmeasured anions. That is why the anion gap calculator is helpful as a quick check, but not a substitute for full clinical interpretation.
Keep in mind that lab reference ranges can vary by method, but the overall concept remains the same. The anion gap helps answer a practical question: are there extra acids in the bloodstream that are not reflected directly in the standard electrolyte panel?
Why the Anion Gap Matters in Ketoacidosis
Ketoacidosis is a state in which ketones accumulate enough to cause metabolic acidosis. In this setting, the body produces organic acids, and those acids lead to high anion gap metabolic acidosis. The gap rises because ketones act as unmeasured anions.
This is especially important in diabetic ketoacidosis, where insulin deficiency leads to ketone production, dehydration, and worsening acid-base disturbance. As ketones build up, bicarbonate is consumed buffering the acid load, and acidemia appears. The result is a pattern that often includes a low serum bicarbonate, elevated anion gap, and a low pH on blood gas testing.
The anion gap matters because it helps distinguish ketoacidosis from other forms of metabolic acidosis. A patient can have hyperglycemia, ketones, and acidemia, but the gap provides a more precise picture of severity and underlying mechanism. It also helps with treatment response: as ketones fall, the gap should close if therapy is effective.
From a clinical interpretation standpoint, the gap is not just a number. It reflects the burden of unmeasured anions and the degree of metabolic derangement. In ketoacidosis, a rising anion gap usually means worsening acid buildup, while a closing gap suggests recovery.
How to Determine the Anion Gap
The anion gap formula is usually expressed as:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some clinicians use a version that includes potassium, but the sodium-based formula is the most commonly used because it is simple to use and matches routine laboratory practice. Anion Gap Calculator can handle the arithmetic instantly, but understanding the formula greatly improves interpretation.
When reviewing electrolytes, look at the full serum chemistry picture rather than the gap alone. Sodium, chloride, and bicarbonate each offer clues about the pattern of the acid-base disturbance. For example, a low serum bicarbonate with a high anion gap often indicates accumulation of unmeasured anions rather than a simple isolated electrolyte issue.
Albumin is a major unmeasured anion, so low albumin can make the calculated gap appear falsely normal or only mildly elevated. That is why albumin correction is needed. A corrected anion gap adjusts the measured value upward when albumin is low, uncovering hidden anion gap elevation that might otherwise be missed.
A common correction adds roughly 2.5 mEq/L to the anion gap for each 1 g/dL drop in albumin below normal, though exact formulas may vary. The key point is that albumin changes interpretation. Without correction, you may downplay the severity of high anion gap metabolic acidosis, especially in more ill patients.
So, the calculation is not just math. It is a tool for clinical interpretation that must be integrated with electrolytes, albumin, and the full acid-base picture.
Typical Lab Patterns in DKA
DKA often displays a characteristic picture across glucose, serum bicarbonate, and blood gas results. Blood glucose is often increased, sometimes very, but the defining feature is not hyperglycemia alone. The key feature is the combination of ketone bodies, metabolic acidosis, and a high anion gap.
The bicarbonate is typically low because bicarbonate is consumed buffering the excess acids. An arterial gas often shows low pH and low bicarbonate, with respiratory compensation in the form of a low pCO2. A venous gas may also be helpful for checking pH and bicarbonate in numerous cases, especially when repeated measures are needed during treatment.
Common lab interpretation looks like this:
- Increased blood glucose in numerous, but not each, cases Reduced serum bicarbonate level Elevated anion gap Positive ketones or elevated beta-hydroxybutyrate Acidic blood on arterial blood gas or venous blood gas
Beta-hydroxybutyrate requires particular attention because it is the main ketone in many patients with DKA. Urine ketone tests can downplay severity early on because they may not capture beta-hydroxybutyrate well. A direct beta-hydroxybutyrate level is often more clinically informative for diagnosis and treatment response.
Respiratory compensation is another key clue. Patients often breathe faster to decrease carbon dioxide and partially counterbalance the acid load. That compensation does not resolve the problem, but it helps explain why the pH may be somewhat less severe than expected given the low bicarbonate and high anion gap.
In general, the diagnostic pattern in diabetic ketoacidosis is a high anion gap metabolic acidosis driven by ketones, with lab findings that indicate insulin deficiency and dehydration.
How the Anion Gap Changes During Therapy
Throughout care, the anion gap should start to decline as ketone production drops and existing ketones are cleared. Insulin therapy is the primary driver of this improvement because it suppresses lipolysis and reduces ketone production. As insulin restores metabolic control, beta-hydroxybutyrate falls and gap closure follows.
IV fluids also plays a significant role. Dehydration reduces perfusion and limits renal clearance of acids and ketones, so fluids help improve circulation and support recovery. In many cases, the first signs how to calculate anion gap mEq/L of improvement are seen in the serum chemistry: the gap narrows, bicarbonate begins to rise, and blood glucose trends down with treatment.
It is vital not to focus on blood glucose alone as the marker of recovery. Blood glucose may improve before the ketoacidosis is completely resolved. A patient can have a lower glucose but still have persistent ketones and an elevated anion gap. That is why treatment response should be assessed using the full clinical picture, including acid-base status, beta-hydroxybutyrate, and laboratory trend monitoring.
As the gap closes, repeat testing with an Anion Gap Calculator can help confirm that therapy is working. If the gap remains elevated, clinicians should think about ongoing ketone production, inadequate insulin therapy, persistent dehydration, or another cause of high anion gap metabolic acidosis.
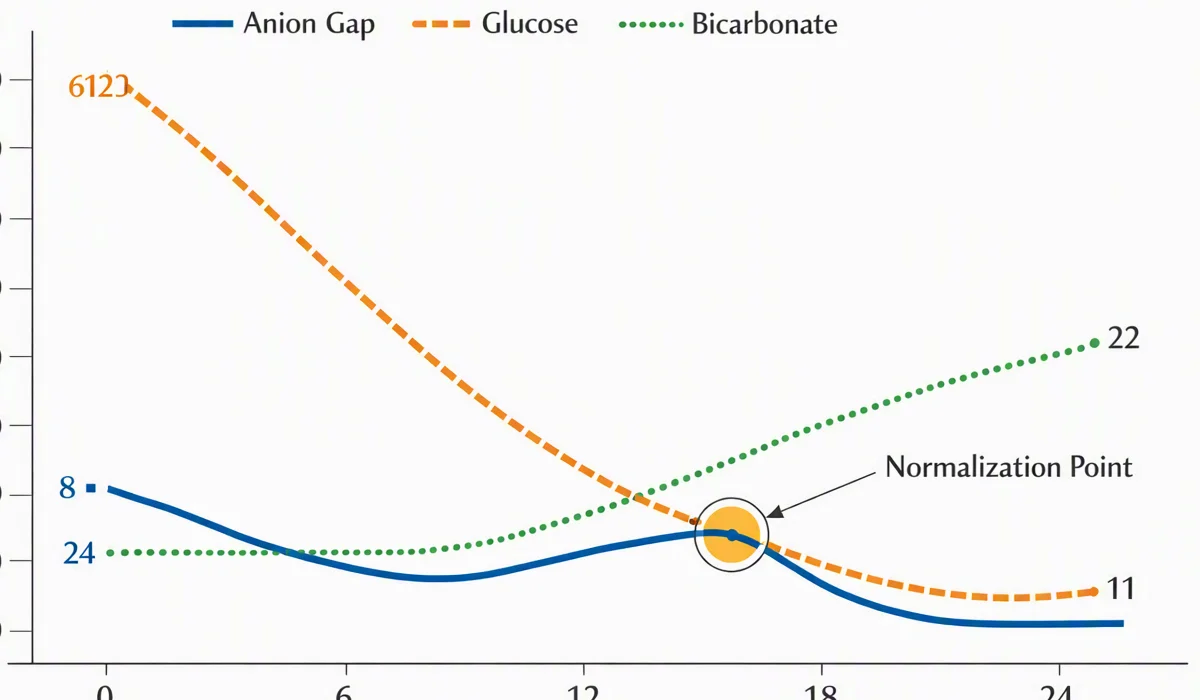
In short, gap closure is a helpful marker of resolution, but it should be interpreted alongside pH, bicarbonate, and the overall lab trajectory.
How to Distinguish Ketoacidosis From Additional Causes of High Anion Gap
Not every high anion gap metabolic acidosis is ketoacidosis. The most useful way to differentiate causes is to match the lab pattern with the clinical context and determine which unmeasured anions are likely present.
Lactic acidosis is a usual alternative cause. It often occurs with hypoperfusion, sepsis, or severe physiologic stress. The lactate level helps identify this cause, and ketones may be absent or only mildly elevated. In ketoacidosis, beta-hydroxybutyrate is usually significantly more prominent.
Renal failure can also cause a high anion gap because retained acids accumulate when kidney excretion is impaired. In that setting, the pattern may intersect with other metabolic derangements, so creatinine, blood urea nitrogen, and clinical history become important.
Toxic alcohols such as methanol or ethylene glycol can produce severe high anion gap metabolic acidosis. They may also cause an osmolar gap early on. The history of ingestion, neurologic findings, and lab screening are critical clues because the presentation can resemble other acidotic states.
Salicylates can create a mixed acid-base disorder with both respiratory alkalosis and metabolic acidosis. That makes interpretation more complicated than simple ketoacidosis. A salicylate level and careful review of arterial blood gas findings are helpful when the story does not fit classic diabetic ketoacidosis.
To differentiate these conditions, ask:
- Are ketones or beta-hydroxybutyrate clearly elevated? Is blood glucose high enough to support diabetic ketoacidosis? Is the lactate elevated enough to explain the gap? Is there evidence of renal failure or toxin exposure? Does arterial blood gas show a mixed pattern?
The best clinical interpretation comes from combining the anion gap with the rest of the workup, not using the number in isolation.
Common Assessment Pitfalls
A typical pitfall is assuming a normal anion gap excludes ketoacidosis. It does not always. Early-stage disease, mixed acid-base disorder, or low albumin can obscure the expected elevation. A patient may still have ketosis and metabolic acidosis even if the gap appears normal at first glance.
Another frequent mistake is forgetting albumin correction. Because albumin contributes to the measured distribution of ions, low albumin can mask a true anion gap elevation. If albumin is low, the corrected anion gap may show clinically meaningful acidosis that the raw value does not capture.
A third mistake is overlooking a mixed acid-base disorder. For example, vomiting can create a metabolic alkalosis that partially balances the acidosis. In that case, pH may look less altered even though the patient has ongoing ketoacidosis. The delta gap can be useful for identifying this situation by comparing the rise in anion gap to the fall in bicarbonate.
The delta gap is especially useful when the clinical picture is confusing. If the gap is elevated more than expected relative to bicarbonate reduction, another metabolic process may be present. If the changes do not match, think about mixed acid-base disorder rather than presuming a single diagnosis.
Lastly, do not rely on a single value. Lab interpretation is best when you review serial values, not just one snapshot. Trends in bicarbonate, beta-hydroxybutyrate, pH, and the anion gap are more revealing than any single result.
Accurate interpretation means understanding the pattern, the correction, and the underlying physiology rather than just plugging numbers into an Anion Gap Calculator.
FAQ: Anion Gap and Ketoacidosis
What anion gap value suggests ketoacidosis?
A value above the local reference range points toward ketoacidosis, especially when it occurs with ketones, low serum bicarbonate, and acidemia. The exact cutoff depends on the laboratory method, so interpretation should use the lab’s normal range and the overall clinical picture rather than a single universal number.
Does a typical anion gap rule out ketoacidosis?
It does not. A standard anion gap cannot completely exclude ketoacidosis. Early illness, albumin correction issues, or a mixed acid-base disorder can hide the elevation. When symptoms and other lab values suggest metabolic acidosis, check ketones, beta-hydroxybutyrate, pH, and bicarbonate closely.
Why do you correct the anion gap for albumin?
Albumin is a major unmeasured anion, so low albumin can make the anion gap look falsely normal or smaller than it really is. Correcting for albumin enhances lab interpretation and helps reveal hidden high anion gap metabolic acidosis.
How does the anion gap change after insulin treatment starts?
With successful insulin therapy, ketone production falls, beta-hydroxybutyrate decreases, and the anion gap should slowly close. Fluid resuscitation also supports recovery by improving perfusion and renal clearance. If the gap does not improve, reassess for ongoing ketoacidosis or another cause of metabolic acidosis.
What other conditions can cause a high anion gap besides ketoacidosis?
Common alternatives include lactic acidosis, renal failure, toxic alcohols, and salicylates. Each has its own diagnostic pattern, so the best approach is to interpret together the anion gap with blood gas results, lactate, kidney function, toxin history, and the overall acid-base balance.