What This Measurement Shows
The anion gap is a helpful way to read blood electrolytes and determine whether the body’s acid base balance may be disrupted. It is not a literal measurement of a single substance. Instead, it is a calculated value that helps detect hidden ions in the blood when examining a standard electrolyte panel.
Clinically, the anion gap is commonly used to investigate metabolic acidosis. This is a metabolic issue in which too much acid builds up or too much bicarbonate is lost. Because the calculation uses routine blood test results, it acts as a practical assessment tool in laboratory interpretation and clinical evaluation.
An Anion Gap Calculator helps users work out anion gap quickly and consistently, especially when they want anion gap with units clearly shown. That matters because the value is only meaningful when the normal ranges and context are understood accurately.
In basic terms, the anion gap reflects the relationship between positively charged and negatively charged particles in blood. The main electrolytes involved are sodium, chloride, and bicarbonate. When the balance shifts, the result can point toward an electrolyte imbalance, an acid-base disorder, or a more specific condition such as high anion gap metabolic acidosis.
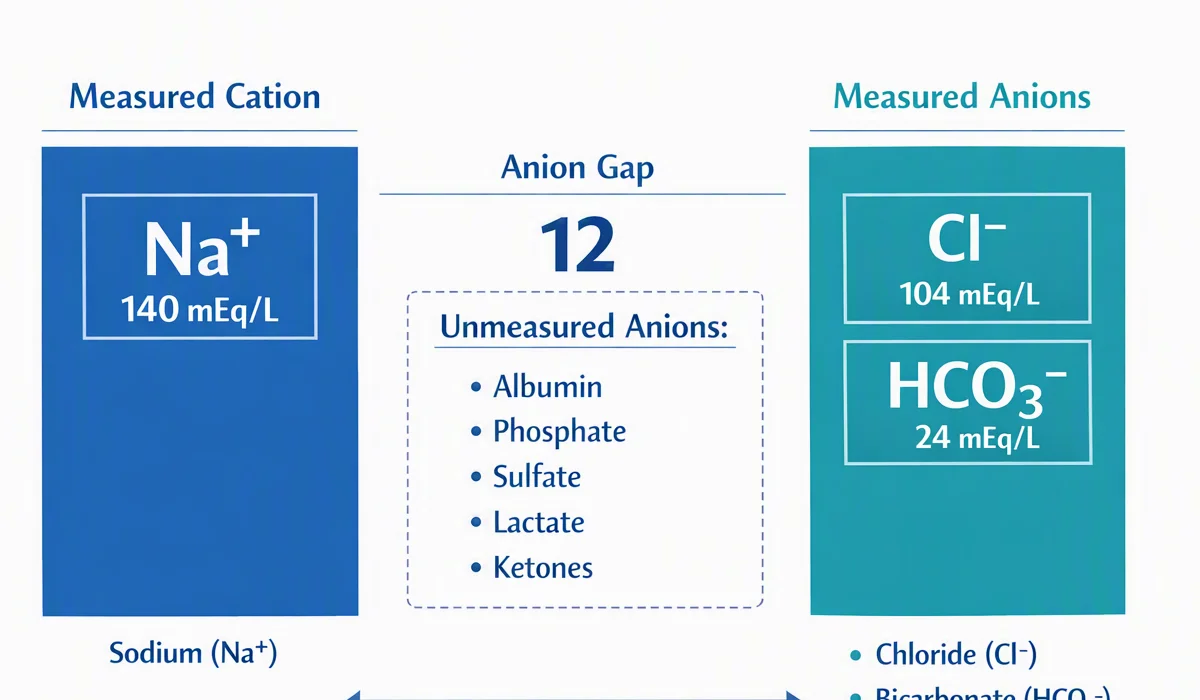
Anion Gap Calculation and Calculation
The standard anion gap equation relies on three typical serum measurements: sodium, chloride, and bicarbonate. The formula is:
Anion gap = sodium − (chloride + bicarbonate)
Certain labs may use a marginally different version that includes potassium, but the most common clinical formula is based on serum sodium, serum chloride, and serum bicarbonate. This is the calculation many people expect from an Anion Gap Calculator.
To determine anion gap step by step:
- Start with the serum sodium value. Add the serum chloride and serum bicarbonate values together. Deduct that total from sodium.
As an example: if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This is the main formula, but interpretation depends on the units, the reference range, and whether albumin correction is needed.
Because anion gap is a computed number rather than a directly measured electrolyte, it should always be interpreted alongside the blood chemistry pattern. A apparently normal number does not always rule out disease, and an abnormal result does not always mean a serious disorder without further context.
Measurement Units Used in Anion Gap Calculation
Anion gap is typically reported in mEq/L or mmol/L. In many cases, these anion gap in chronic kidney disease values are usually numerically equivalent for the electrolytes used in the formula, which is why many clinicians and lab reports treat them similarly. Still, users should always check the laboratory units shown on the report before making assumptions.
The calculation is based on serum chemistry, so the unit formatting matches how the laboratory measures the electrolytes. Sodium, chloride, and bicarbonate are often listed as either mEq/L or mmol/L, depending on the analyzer and reporting system.
For most routine interpretation, anion gap with units does not require conversion if all components come from the same lab report. Consistency is the key point. A calculator should use values from the same electrolyte panel and preserve the same units in the final answer.
Here are the practical takeaways:
- mEq/L is common in clinical chemistry reporting. mmol/L is also widely used and often matches the numeric result. Mixed units can lead to misinterpretation, especially if a value is copied incorrectly.
When using an Anion Gap Calculator, always verify the units before reviewing the interpretation. Even though the formula is simple, the reliability of the result depends on accurate blood chemistry data and correct laboratory units.
Normal Anion Gap Range and Reference Values
The typical range for anion gap differs by laboratory because various analyzers and reference methods may give slightly different results. For this reason you should rely on the lab’s published range rather than a single universal number.
In many settings, the anion gap is viewed normal when it falls within a small range centered around the low teens, but the exact reference values change. Some reports also adapt interpretation based on whether potassium is included in the formula. Because of these differences, the numeric result should consistently be compared with the local lab’s published values.
Albumin plays an essential role in the normal range. Since albumin is a major unmeasured anion, a low albumin level can make the anion gap appear lower than expected. This is why albumin correction may be needed when interpreting blood test results in patients with low albumin.
The corrected anion gap is often more helpful than the raw number when albumin is reduced. This adjustment helps reduce missed recognition of an underlying acid-base disorder. If albumin is low, a seemingly normal anion gap can conceal a real abnormality.
Reference values should always be interpreted in context:
- Apply the lab-specific reference range. Determine whether the result is uncorrected or corrected. Assess albumin level before drawing conclusions.
High Anion Gap vs Normal Anion Gap Metabolic Acidosis
One of the key applications of the anion gap is distinguishing high anion gap metabolic acidosis from normal anion gap metabolic acidosis. Each are varieties of metabolic acidosis, but they stem from different mechanisms and therefore indicate other causes.
In high anion gap metabolic acidosis, additional acids gather in the body. These acids are not directly measured in the routine electrolyte panel, so the anion gap increases. Common examples include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
In normal anion gap metabolic acidosis, bicarbonate is depleted and replaced by chloride, so the gap remains within the expected range. This is also called hyperchloremic metabolic acidosis. The acid-base balance is still abnormal, but the pattern is unlike from high-gap states.
Lactic acidosis is a common cause of high anion gap metabolic acidosis. It can occur when tissues are not receiving enough oxygen or when metabolism is significantly stressed. Ketoacidosis is another classic cause, especially when the body produces too many ketones. Renal failure can also cause accumulation of acids because the kidneys cannot remove them properly.
By contrast, normal anion gap metabolic acidosis is often associated with bicarbonate loss from the gastrointestinal tract or kidneys. The chloride shift helps keep electrical neutrality, so the gap may look normal even though the patient has a substantial acid-base disorder.
Common Causes of an Abnormal Anion Gap
An abnormal anion gap can suggest several relevant clinical issues, but the meaning depends on whether the result is increased or low. For clinical practice, the most relevant abnormality is a high value.
Ketone-related acidosis is a typical cause of elevated anion gap. This may arise in diabetes, starvation, or other metabolic states where ketone production increases. These acids widen the gap because they add unmeasured anions to the bloodstream.
Renal failure can also raise the anion gap by impairing acid excretion. As kidney function worsens, acids collect, and the calculated gap increases.
Exposure to toxins is another key cause. Certain toxic substances generate unmeasured acids or interfere with metabolism, leading to increased anion gap metabolic acidosis. In clinical evaluation, this possibility should be taken into account when the blood chemistry pattern is unusual or marked.
Elevated lactate acidosis is often seen in sudden illness, poor tissue perfusion, or systemic stress. It is one of the most important causes to identify quickly because it may signal a severe underlying problem.
Bicarbonate loss is more often seen in normal anion gap metabolic acidosis. While the gap may not be elevated, the bicarbonate level is lowered, and the clinical impact can still be notable.
Other causes and contributors can include mixed acid-base disorders, medication effects, and changes in serum electrolytes. This is why an increased or low anion gap should never be interpreted in isolation.
How to Interpret Results Correctly
Proper interpretation means looking beyond a number and the reference range. A thoughtful clinical interpretation should consider albumin, the delta ratio for mixed metabolic and respiratory electrolyte pattern, and the likely acid-base disorder.
Initially, review albumin correction if the patient has low albumin. Since albumin affects the anion gap, reduced levels can hide a clinically relevant elevation. The corrected anion gap gives a better estimate of the true acid-base status in many cases.
Then, look for a chloride shift. If bicarbonate is low and chloride is high, the pattern may indicate normal anion gap metabolic acidosis. This does not exclude disease; it only suggests a different mechanism than high-gap states.
Also, connect the result with the broader acid-base disorder. The anion gap is one part of the story. It should be interpreted with pH, bicarbonate, clinical symptoms, and other relevant laboratory findings when available.
A useful approach is to think in layers:
- Is the anion gap high, standard, or low? Do sodium, chloride, and bicarbonate fit together logically? Is albumin decreased enough to warrant correction? Does the overall pattern fit the patient’s presentation?
Using this approach helps reduce common errors in interpretation. A result should help confirm the diagnosis, not substitute for clinical judgment.
When to Use an Anion Gap Calculator
An Anion Gap Calculator can be most useful if you have laboratory values from an electrolyte panel and want a fast, reliable way to calculate the anion gap. It is especially valuable during a medical assessment as rapid blood chemistry review is needed.
Rely on a calculator when reviewing lab values that include sodium, chloride, and bicarbonate. These results are usually available in a standard electrolyte panel and can be entered directly without math errors.
A calculator is also useful when comparing multiple sets of blood test results over time. Trend analysis can reveal whether the gap is increasing, falling, or remaining stable. That can be useful in monitoring treatment response or identifying a worsening metabolic disturbance.
In clinical workflows, the calculator serves as a practical support tool for laboratory interpretation. It can help clinicians, students, and patients understand the relationship between serum electrolytes and acid-base balance. It is not a substitute for professional diagnosis, but it can improve clarity when reviewing blood chemistry results.
It is worth using when:
- Assessing possible metabolic acidosis Checking for high anion gap metabolic acidosis Reviewing low albumin and thinking about albumin correction Checking an unexplained electrolyte imbalance
Frequently Asked Questions
What is the formula for calculating anion gap?
The standard formula is sodium minus the sum of chloride and bicarbonate. In equation form, it is anion gap = sodium − (chloride + bicarbonate). This is the most common formula used by an Anion Gap Calculator.
What units are used for anion gap?
Anion gap is commonly reported in mEq/L or mmol/L. In many cases, the numeric result is the same in both formats, but you should always follow the laboratory units shown on the report.
What is a normal anion gap range?
The normal range depends on the laboratory reference range and the testing method used. Always compare the result with the local reference values rather than assuming one universal normal range.
How does low albumin affect the anion gap?
Low albumin can decrease the calculated anion gap because albumin is a key unmeasured anion. That is why albumin correction is important; the corrected anion gap may show an abnormality that the uncorrected value conceals.
What does a high anion gap indicate?
A high anion gap often suggests high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion. The result should always be read with the full clinical picture and other blood test results.