What Means the Anion Gap?
The anion gap is a calculated value that guides clinicians analyze acid-base balance by contrasting measured serum sodium against measured serum chloride and serum bicarbonate. It is not a directly measured lab result. Instead, it is a helpful diagnostic marker generated from a standard chemistry panel, often supported by an anion gap calculator for quick clinical interpretation.
At a fundamental level, the anion gap reflects the difference between the positively charged ions and the negatively charged ions reported in routine serum electrolytes. Because the body must remain electrically balanced, this gap can reveal hidden acids in the blood when the balance shifts. That is why the anion gap is often part of the evaluation for metabolic acidosis and other acid-base disorder patterns.
The commonly used calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
When the value is elevated, it often indicates unmeasured acids in the bloodstream. When it is normal, it does not always mean the patient is stable, but it does narrow the differential diagnosis. In practice, the anion gap is one of the best tools for reviewing laboratory values in the setting of illness, dehydration, or suspected metabolic derangement.
How come the Anion Gap Calculator Is Significant in Diabetic Ketoacidosis
diabetic ketoacidosis is a common cause of high anion gap metabolic acidosis. In diabetic ketoacidosis, the body cannot use glucose properly because of a lack of insulin, so it begins breaking down fat for fuel. This process produces ketone bodies, including beta-hydroxybutyrate, which collect and drive anion gap increase.
As ketones rise, they increase ketone load and deplete bicarbonate, which contributes to bicarbonate loss and a declining serum bicarbonate level. The result is worsening acidosis and a distinct disturbance in acid-base balance. A patient with DKA may also have dehydration, electrolyte imbalance, and worsening acidosis progression, all of which affect the clinical picture.
The anion gap calculation helps separate DKA from other causes of metabolic acidosis. It is especially useful when symptoms are nonspecific or when a blood gas has not yet been obtained. Together with glucose, ketones, and the electrolyte panel, it helps confirm the diagnosis and track how severe the metabolic derangement is.
Because DKA can develop rapidly, an anion gap calculator can be a useful way to read the chemistry profile in real time. It does not substitute for clinical judgment, but it aids better clinical interpretation when reading serum electrolytes, blood gas results, and ketone testing together.
How to Calculate the Anion Gap
The standard anion gap formula uses the sodium level, chloride level, and bicarbonate level values from an electrolytes panel. The majority of formulas omit potassium, although some clinicians consider it in specific contexts. A typical calculation is:
Anion gap = sodium - (chloride + bicarbonate)
For example, if serum sodium is 140, serum chloride is 100, and serum bicarbonate is 12, the anion gap is 28. That degree of elevation strongly indicates an acid load from unmeasured anions, such as ketones in DKA.
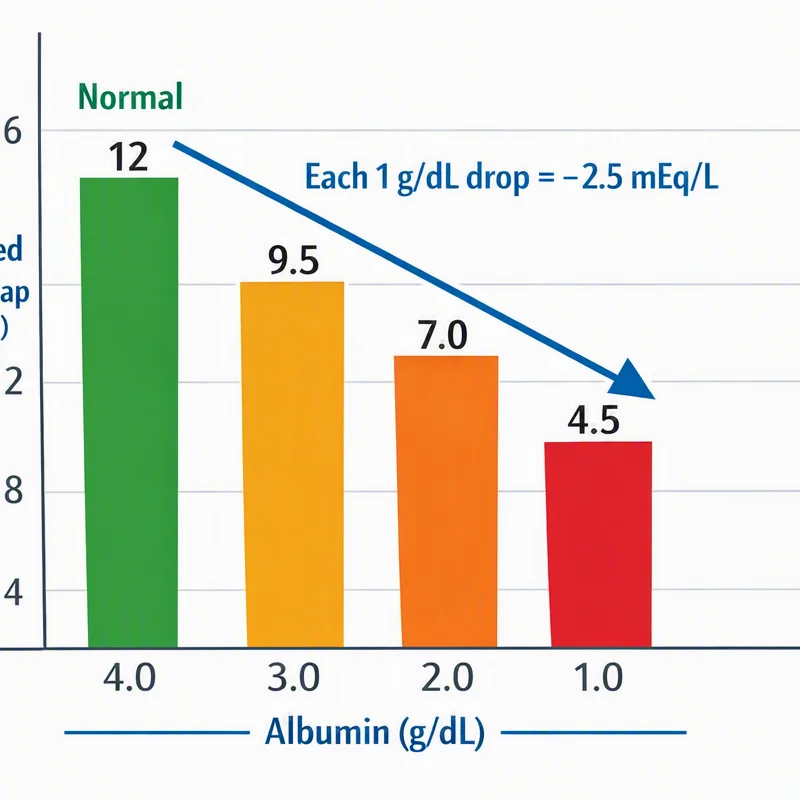
However, the raw number may be misleading when albumin is low. Albumin is a important unmeasured anion, so low albumin can make the anion gap look falsely normal or only mildly elevated. That is why a corrected anion gap is often used when interpreting metabolic acidosis. This adjustment improves accuracy, especially in critically ill patients, where protein levels may be altered.
Using an anion gap calculator can streamline the process, especially when it includes albumin correction. A corrected value is often more useful for deciding whether the patient has ongoing acid retention or whether the measured gap is being masked by hypoalbuminemia. This is important in both diagnosis and monitoring trend over time.
In DKA, the calculation should always be interpreted alongside the blood gas, potassium, glucose, ketones, and the overall clinical picture. The number alone is helpful, but the pattern matters more than a single result.
Usual Anion Gap Values in DKA
A normal anion gap usually falls within the laboratory expected range, though exact thresholds vary by method and instrument. Many labs report values near 8 to 12 mEq/L, but the accepted range depends on the local blood chemistry system and the lab’s calibration. As a result, clinicians should always use the reference interval from the reporting laboratory.
In high anion gap metabolic acidosis, the anion gap is raised because unmeasured acids are present in excess. DKA is one of the classic examples. The greater the gap, the more likely there is significant ketone accumulation, though the degree of elevation does not always perfectly match symptom severity.
Blood chemistry in DKA often shows:
- Elevated glucose Decreased serum bicarbonate Fluctuating serum chloride Alterations in potassium Elevated ketones, especially beta-hydroxybutyrate
It is important to remember that the anion gap is a sign, not a diagnosis by itself. DKA is usually confirmed by the combination of hyperglycemia, ketones, and metabolic acidosis. When read carefully, the anion gap helps confirm the presence of an acid burden and helps guide the urgency of treatment.
How the Anion Gap Changes During DKA Treatment
As treatment begins, the anion gap should generally decrease if the therapy is working. This movement reflects ketone clearance, which occurs as insulin therapy ends ongoing ketone production and helps the body use glucose again. Intravenous fluids also support circulation, decrease dehydration, and support renal clearance of acids and ketones.
During recovery, serum bicarbonate typically rises as acid production falls and buffering gets better. This is often described as bicarbonate recovery. A closing anion gap is one of the clearest signs that the metabolic acidosis from DKA is getting better.
That said, the anion gap may not normalize immediately, especially if ketone bodies remain in circulation or if treatment has only partially treated the underlying problem. Monitoring trend is more helpful than relying on a single repeat value. Clinicians often follow the electrolyte panel and blood gas together to assess treatment response.
It is also common for potassium to change during therapy. Even if potassium is normal or high at presentation, it may fall after insulin and fluids begin. This does not directly determine the anion gap, but it is a critical part of the overall acid-base and electrolyte picture.
In short, declining anion gap values usually indicate that treatment is working. Rising or persistent values suggest ongoing acid generation, incomplete ketone clearance, or another cause of acidosis that deserves review.
Anion Gap vs. Bicarbonate: What is the Distinction?
The anion gap and bicarbonate are connected but not identical. Bicarbonate reflects one part of the body’s buffering system, while the anion gap indicates the presence of extra acids. Both are essential to understanding acid-base status, but they answer different questions.
A low bicarbonate level tells you that acidosis is present or that the buffer has been depleted. A raised anion gap tells you that the acidosis is probably caused by unmeasured ions such as ketones, lactate, or toxins. In DKA, both are often off at the same time.
This separation matters because other acid-base disorders can seem alike at first glance. For example, lactic acidosis can also raise the anion gap, and a patient may have both DKA and lactic acidosis at the same time. Blood gas results, lactate testing, and the clinical context help clarify the cause.
Think of bicarbonate as the “what is low?” number and the anion gap as the “what is accumulating?” number. In tandem they provide a much more complete view of the patient’s metabolic state than either value alone. This is why the anion gap calculator is so valuable in practice: it helps relate the chemistry profile to the underlying physiology.

When a Normal Anion Gap Does Not Eliminate DKA
A standard anion gap may not always exclude DKA. This represents one of the most important pitfalls in interpretive interpretation. A patient can have a mixed acid-base disorder, where one process elevates the gap while another reduces it. As a result, the final number may appear falsely normal.
One common reason is hyperchloremia. https://ameblo.jp/anion-gap-results311/entry-12977185501.html During treatment or due to fluid shifts, chloride can climb and offset the unmeasured anions, producing hyperchloremic acidosis. In this setting, ketones may still be present, but the gap no longer looks elevated in the expected way.
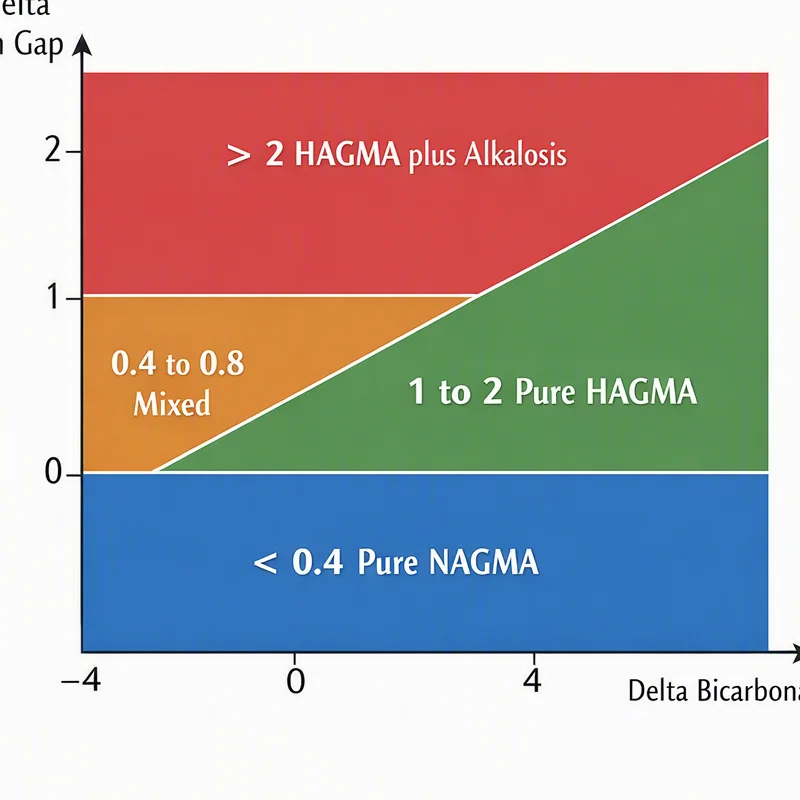
The delta gap can help identify this problem. It compares the change in anion gap to the change in bicarbonate and helps reveal whether more than one acid-base process is occurring. If the relationship does not fit typical DKA, a complex disorder should be considered.
Persistent ketosis is another clue. A normal gap may coexist with ongoing ketone production, especially if treatment has started but has not fully corrected the underlying insulin deficiency. That is why ketones, blood gas, and electrolyte values all should be considered together. A single normal gap should never end the evaluation when the clinical picture still suggests DKA.
Frequent Errors When Interpreting the Anion Gap
One common mistake is forgetting albumin correction. Low albumin can conceal a true anion gap elevation and lead to underestimation of the severity of metabolic acidosis. This is especially relevant in critically ill patients or those with poor nutrition, inflammation, or prolonged illness.
A further pitfall is assuming all elevated gaps is DKA. Although DKA is a leading cause, other problems such as lactic acidosis, kidney failure, or toxin exposure can also increase the gap. Careful clinical interpretation is required to identify the true cause of the acid-base disorder.
Lab variation also matters. Different laboratories may use slightly different methods, producing different reference interval cutoffs. This is why the same patient can appear to have a different gap depending on where the blood chemistry is processed.
A further issue is ignoring broader electrolyte imbalance. Sodium, chloride, bicarbonate, and potassium all affect the interpretation. If one value is shifting because of fluids, renal function, or treatment, the anion gap may change in ways that reflect therapy rather than disease progression.
In the end, clinicians sometimes rely too heavily on the number alone. A good diagnostic interpretation requires the anion gap, ketones, glucose, blood gas, lactate, albumin, and the clinical presentation. The anion gap calculator is most helpful when it is used as part of that larger assessment rather than as a stand-alone answer.
Frequently Asked Questions About the Anion Gap in DKA
What does a high anion gap mean in diabetic ketoacidosis?
A high anion gap in diabetic ketoacidosis usually means that unmeasured acids, mainly ketone bodies such as beta-hydroxybutyrate, are accumulating in the blood. This pattern supports high anion gap metabolic acidosis and helps confirm the diagnosis when combined with glucose, ketones, and blood gas results.
What range is considered normal for the anion gap?
The normal anion gap range depends on the laboratory reference interval, but many labs report a value roughly around 8 to 12 mEq/L. The exact cutoff can vary because of lab methods, so the reporting lab’s range should always be used when interpreting serum electrolytes.
How do you determine the anion gap with albumin correction?
You first compute the usual anion gap using sodium minus chloride plus bicarbonate. Then you adjust for albumin because low albumin can hide a true elevation. A corrected anion gap gives a more precise estimate of the acid burden when albumin is low, enhancing clinical interpretation.
Can diabetic ketoacidosis happen with a normal anion gap?
Yes. DKA can sometimes present with a normal anion gap if there is a mixed acid-base disorder, hyperchloremic acidosis, or partially treated ketosis. Persistent ketosis may still be present even when the gap is no longer elevated, so the full electrolyte panel and blood gas should be checked.
How does the anion gap change after DKA treatment starts?
As insulin therapy and intravenous fluids begin working, the anion gap usually drops because ketone clearance improves and bicarbonate recovery begins. A falling gap is a helpful sign of treatment response, but the trend should be interpreted alongside potassium, ketones, and other laboratory values.